




















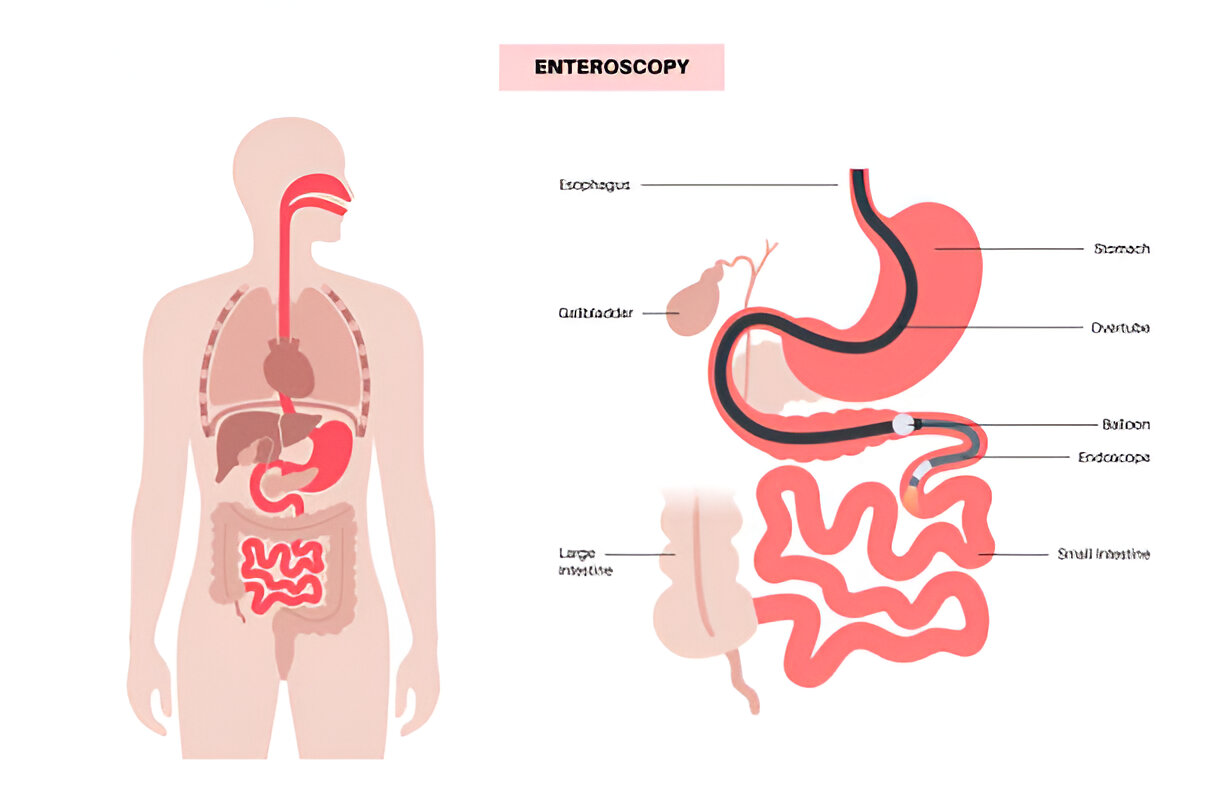
- What it is: A rare disorder in which the lower esophageal sphincter fails to relax and the esophagus loses its normal squeezing movement, so food and liquid do not pass easily into the stomach.
- Common symptoms: Trouble swallowing solids and liquids, regurgitation of food, chest pain, heartburn-like discomfort and weight loss.
- Conventional care: Tests such as endoscopy and manometry, then a procedure that opens the sphincter, such as pneumatic dilation, peroral endoscopic myotomy or Heller myotomy.
- How integrative care fits: Supportive care for stress, comfort and general well-being after the condition is under a specialist's management; it does not treat the sphincter problem.
- Evidence at a glance: Very limited for acupuncture and Ayurveda in achalasia itself, with no controlled trials we could verify; limited for Chinese medicine added to balloon dilation, from trials with risk of bias.
What is Achalasia?
Achalasia is a disorder of the esophagus in which the lower esophageal sphincter does not relax properly and the muscle of the esophagus loses its normal wave-like movement.[1, 2] This blocks the passage of food into the stomach. It is uncommon, and it is a condition that needs diagnosis and treatment by a specialist.[1]
Common symptoms
The most common symptom is trouble swallowing both solids and liquids, often with regurgitation of undigested food and sometimes chest pain or weight loss.[2, 3] Some people have heartburn-like symptoms that do not respond to acid-lowering medicine.[4]
Symptoms usually build slowly. Several years can pass between the first symptoms and the diagnosis.[3] Regurgitated food can also be breathed into the lungs, which is why night-time coughing deserves attention.[1]
Causes and risk factors
The key problem is loss of the nerve cells that tell the sphincter to relax. Researchers think this probably results from an autoimmune attack on the nerves of the esophagus wall.[3] The exact trigger is still not known. Achalasia becomes more common with age, but it can affect any age and both sexes.[3]
Chagas disease, a parasitic infection found mainly in parts of Central and South America, can cause a similar picture.[1]
How it is diagnosed and treated conventionally
Evaluation usually starts with an upper endoscopy to rule out a blockage or other cause. High-resolution manometry, which measures pressures in the esophagus, then confirms the diagnosis, and a barium swallow X-ray can add information.[2, 5]
Pills that relax the sphincter are not particularly effective. Botulinum toxin injection can give temporary relief, and longer-lasting treatment comes from pneumatic (balloon) dilation, laparoscopic Heller myotomy or peroral endoscopic myotomy (POEM).[3, 6] In a systematic review, balloon dilation was effective in 70% to 90% of patients and laparoscopic myotomy in 88% to 95%, with outcomes depending on the achalasia subtype.[4] Rarely, long-standing achalasia is followed by esophageal cancer, so ongoing follow-up with your specialist matters.[3]
Why Achalasia calls for a whole-person approach
Achalasia is first a problem of nerves and muscle in the esophagus, and no complementary therapy has been shown to correct it. Still, the condition affects eating, weight, sleep and mood, and these are areas where supportive care can be considered alongside specialist treatment.[4]
The factors below are the ones most closely tied to daily life with achalasia.
Nerve and immune changes
Loss of the inhibitory nerves of the esophagus is the central mechanism, and an autoimmune process is the leading explanation.[3] This is why treatment is aimed at the sphincter itself, and why we do not claim to influence it.
Eating, weight and nutrition
Trouble swallowing can lead to weight loss, and food that stays in the esophagus causes regurgitation and discomfort.[2, 3] Eating habits, meal size and food texture are worth discussing with your gastroenterologist or a dietitian.
Reflux-type symptoms after treatment
Heartburn-like symptoms that do not respond to reflux treatment can be a presenting sign of achalasia.[4] In a meta-analysis of trials combining Chinese medicine with balloon dilation, reflux was less frequent than with dilation alone, although the authors advised caution because of risk of bias.[7]
Quality of life and stress
Achalasia can significantly reduce quality of life.[4] Living with a long-term swallowing problem can be stressful, and stress and anxiety are symptoms that some supportive therapies have been studied for, as described below.
Acupuncture as supportive care in Achalasia
What the research shows
There are no controlled trials of acupuncture for achalasia that we could verify. A PubMed search found a few older reports from China, including a 1994 clinical trial and case reports, but they had no available abstracts, so we cannot describe their results. Evidence for acupuncture in achalasia itself is therefore very limited.
A related condition is not the same disease. Achalasia of the cricopharyngeus muscle after a stroke affects the upper esophagus, not the lower sphincter. A meta-analysis of 10 trials with 517 patients found that acupuncture added to balloon dilation improved swallowing scores in that stroke-related problem.[8] A larger meta-analysis of 39 trials found better swallowing outcomes with acupuncture after stroke in general.[9] These results come from stroke patients and cannot be applied to achalasia of the lower esophagus.
How acupuncture may work
For achalasia, we do not know of research showing how acupuncture would act on the lower esophageal sphincter. Any effect on comfort, relaxation or stress would be a general one and has not been tested in this condition.
What treatment involves
Treatment uses fine, sterile, single-use needles, usually left in place for about 20 to 40 minutes, over a short course of visits with reassessment. Needle placement is chosen with your symptoms in mind, and we avoid the chest and upper abdomen when you have a recent procedure or healing area.
Serious problems from acupuncture are rare. In prospective studies, about 9 in 100 patients had a minor reaction such as bleeding, soreness or a flare at a needle site, and serious events occurred in about 1 in 10,000 patients.[10] Tell the practitioner first if you have a bleeding disorder, take blood thinners, are pregnant, or have a pacemaker (relevant to electroacupuncture).
Ayurvedic medicine as supportive care in Achalasia
The Ayurvedic view
Ayurveda has no single classical name for achalasia. A published Ayurvedic case report describes the symptoms as caused by impaired Vata and aims treatment at restoring downward movement (vatanulomana).[11] This is a traditional framework and not a biomedical diagnosis.
Therapies that may be used
Care is individual and traditionally combines:
- Diet and daily routine, such as warm, soft, regular meals eaten slowly, matched to what your specialist advises
- Gentle oil massage for relaxation
- Individually prescribed herbs, chosen with attention to your medicines and your swallowing ability
Panchakarma is not appropriate during pregnancy, acute illness or frailty, or when you cannot swallow safely or are losing weight. Procedures that induce vomiting are unsuitable in achalasia because of the risk of aspiration.
What the research shows
The research is very limited. A PubMed search found one published case report: a single patient with two years of symptoms who improved over a month of Ayurvedic treatment and stayed symptom-free over three months of follow-up.[11] A single case cannot show that a treatment works. We found no trials.
Ayurvedic herbs such as ashwagandha have been studied for stress and anxiety in general. A meta-analysis of 12 randomized trials found lower anxiety and stress scores than with placebo, but the certainty of the evidence was low and the results varied widely between trials.[12] These trials were not in people with achalasia.
Herbal medicine as supportive care in Achalasia
Herbs and formulas that have been studied
In China, Chinese medicine has been combined with balloon dilation for achalasia in clinical trials. The review's abstract does not say which formulas or herbs were used, and any herb at our clinic would be prescribed individually by a qualified practitioner.[7] In the laboratory, Coptis chinensis (huang lian) and its component berberine relaxed lower esophageal sphincter tissue that had been made to contract.[13]
What the research shows
The evidence is limited. A meta-analysis of 10 randomized trials with 504 patients found that Chinese medicine plus balloon dilation led to more improvement at 1 year and 5 years than balloon dilation alone, and less reflux. The authors advised caution because of risk of bias.[7]
The Coptis and berberine work was a laboratory study on tissue, not a clinical trial. It shows a possible mechanism and does not show that taking the herb helps patients.[13] None of this replaces dilation, myotomy or POEM.
Safety and herb-drug interactions
Herbs are active substances and can interact with medicines. Reviews describe bleeding when warfarin is combined with some herbs, and other interactions with drugs for the heart, diabetes and mood.[14] If you take calcium channel blockers or nitrates for achalasia, tell us, because we will not add anything that could affect them without your physician's knowledge.
In one study, about one fifth of Ayurvedic products bought online contained detectable lead, mercury or arsenic.[15] Herbs should come from tested sources. Tell us if you are pregnant or breastfeeding or have liver or kidney disease. Tablets and capsules can also be hard to swallow with achalasia, so tell us about any swallowing difficulty.
Translating traditional medicine into modern biological language
This is interpretation, not equivalence. Chinese medicine may describe swallowing difficulty as stagnant qi or obstruction in the chest and stomach, and Ayurveda describes impaired Vata, the principle of movement.[11] Researchers describe achalasia as a loss of inhibitory nerve signals to the esophagus, probably through an autoimmune attack.[3]
The Coptis and berberine laboratory work, which points to potassium channels as one route of sphincter relaxation, shows how a traditional herb can be studied in these terms.[13] No study has shown that qi or Vata corresponds to a specific biological process.
How this care fits with your medical care
Complementary care for achalasia is supportive only. For a condition like this, we ask that you are under a physician's care for it and that your treating team knows you are receiving complementary care. Keep your gastroenterologist or surgeon, keep your follow-up appointments, and do not stop or change prescribed treatment without your prescriber.
We do not diagnose achalasia or manage the esophagus. Please bring your diagnosis, manometry, endoscopy or barium reports, a list of medicines and supplements, and details of any dilation, injection or surgery.
When to seek urgent medical care
Some symptoms of achalasia need prompt assessment by your physician or emergency care.
- Food that will not pass, or being unable to swallow your own saliva
- Coughing, choking or breathlessness after regurgitation, or fever with cough
- Chest pain that is severe or comes with sweating, breathlessness or pain spreading to the arm or jaw
- Vomiting blood or black stools
- Rapid or unexplained weight loss
- New or worsening trouble swallowing after a dilation or surgery
For emergencies, call 911 or go to the nearest emergency department.
Frequently asked questions
What is achalasia?
Achalasia is a rare disorder of the esophagus in which the lower esophageal sphincter does not relax and the esophagus loses its normal movement. Food and liquid have trouble reaching the stomach. People notice trouble swallowing, regurgitation, chest pain or weight loss. It is thought to involve loss of nerve cells in the esophagus wall, and it needs specialist treatment.
Can acupuncture help people with achalasia?
There are no controlled trials of acupuncture for achalasia that we could verify, so evidence is very limited. Studies in people with swallowing problems after a stroke are a different condition and do not apply directly. Acupuncture may be used for general comfort and stress alongside your specialist’s treatment, but it does not open the sphincter.
Can Ayurvedic or herbal medicine treat achalasia?
Not on its own. Ayurveda has only a single published case report for achalasia. A meta-analysis of trials in China combining Chinese medicine with balloon dilation suggests added benefit, but the studies carry risk of bias and the abstract does not name the herbs used. Herbs can interact with medicines and can be hard to swallow, so any herb must be prescribed individually and checked with your physician.
Can I skip dilation, POEM or surgery if I use complementary care?
No. Pneumatic dilation, myotomy and POEM are the treatments shown to open the sphincter, and complementary care has not been shown to replace them. Do not stop or change prescribed treatment without your physician. We offer supportive care only, with your treating team informed.
What should I bring to my first visit?
Bring your diagnosis and test reports such as endoscopy, manometry or barium swallow, a full list of medicines and supplements, and details of any dilation, botulinum toxin injection or surgery. Tell us about any trouble swallowing pills, weight loss or coughing after meals, so your care can be planned around them.
Does insurance cover acupuncture for achalasia?
It may. Netra Integrative Health Clinic accepts most major insurance plans that include out-of-network acupuncture benefits, for example Aetna, Blue Cross Blue Shield, Cigna and UnitedHealthcare, and offers a free benefits check. HSA and FSA cards and CareCredit are also accepted. Call (908) 402-7301 to ask about your plan.
References
- Puri R, Tian C. Achalasia. StatPearls [Internet]. 2026. PMID 30137800. StatPearls chapter on achalasia describing failed sphincter relaxation, absent peristalsis, progressive dysphagia to solids and liquids, and rising reported prevalence.
- Vaezi MF, Pandolfino JE, Yadlapati RH, et al. ACG Clinical Guidelines: Diagnosis and Management of Achalasia. Am J Gastroenterol. 2020;115(9):1393-1411. PMID 32773454. American College of Gastroenterology guideline on diagnosing and treating achalasia, covering symptoms, manometric subtypes and endoscopic and barium findings.
- Savarino E, Bhatia S, Roman S, et al. Achalasia. Nat Rev Dis Primers. 2022;8(1):28. PMID 35513420. Nature Reviews Disease Primers overview of achalasia covering autoimmune nerve loss, symptoms, diagnosis, ineffective oral drugs and the main procedures, and the rare cancer risk.
- Pandolfino JE, Gawron AJ. Achalasia: a systematic review. JAMA. 2015;313(18):1841-52. PMID 25965233. JAMA systematic review of achalasia: diagnosis, subtype-based outcomes, and the effectiveness of pneumatic dilation and laparoscopic myotomy in randomized trials.
- Pomenti S, Blackett JW, Jodorkovsky D. Achalasia: Diagnosis, Management and Surveillance. Gastroenterol Clin North Am. 2021;50(4):721-736. PMID 34717867. Gastroenterology Clinics review of diagnosis, management and surveillance of achalasia, naming manometry as the diagnostic standard and listing definitive treatments.
- Oude Nijhuis RAB, Zaninotto G, Roman S, et al. European guidelines on achalasia: United European Gastroenterology and European Society of Neurogastroenterology and Motility recommendations. United European Gastroenterol J. 2020;8(1):13-33. PMID 32213062. European guideline on achalasia with recommendations on definition, tests, medical, endoscopic and surgical therapy, follow-up and esophageal cancer risk.
- Chen J, Huang X, Li Y, et al. Efficacy and safety of Chinese medicine combined with balloon dilatation vs. balloon dilatation alone for achalasia patients: a systematic review and meta-analysis. Ann Transl Med. 2022;10(6):275. PMID 35433949. Meta-analysis of 10 randomized trials (504 patients) finding Chinese medicine plus balloon dilation improved outcomes and reflux versus dilation alone, with risk-of-bias cautions.
- Luo J, Huang B, Zheng H, et al. Acupuncture combined with balloon dilation for post-stroke cricopharyngeal achalasia: A meta-analysis of randomized controlled trials. Front Neurosci. 2022;16:1092443. PMID 36711135. Meta-analysis of 10 trials (517 patients) of acupuncture plus balloon dilation for post-stroke cricopharyngeal achalasia, a different condition, showing better swallowing scores.
- Lu Y, Chen Y, Huang D, et al. Efficacy of acupuncture for dysphagia after stroke: a systematic review and meta-analysis. Ann Palliat Med. 2021;10(3):3410-3422. PMID 33849125. Meta-analysis of 39 randomized trials finding acupuncture improved swallowing outcomes after stroke, a different cause of dysphagia.
- Bäumler P, Zhang W, Stübinger T, et al. Acupuncture-related adverse events: systematic review and meta-analyses of prospective clinical studies. BMJ Open. 2021;11(9):e045961. PMID 34489268. Systematic review of 21 prospective studies finding minor acupuncture reactions in about 9 percent of patients and serious events in about 1 per 10,000.
- Rastogi S, Chaudhari P. Ayurvedic management of achalasia. J Ayurveda Integr Med. 2015;6(1):41-4. PMID 25878463. Single Ayurvedic case report of achalasia treated as impaired Vata, with symptom-free follow-up at three months.
- Akhgarjand C, Asoudeh F, Bagheri A, et al. Does Ashwagandha supplementation have a beneficial effect on the management of anxiety and stress? A systematic review and meta-analysis of randomized controlled trials. Phytother Res. 2022;36(11):4115-4124. PMID 36017529. Meta-analysis of 12 randomized trials of ashwagandha finding reduced anxiety and stress versus placebo, with low-certainty evidence and high heterogeneity.
- Koh WH, Lin LW, Lin TI, et al. Exploring the relaxation effects of Coptis chinensis and berberine on the lower esophageal sphincter: potential strategies for LES motility disorders. BMC Complement Med Ther. 2024;24(1):417. PMID 39696287. Laboratory study showing Coptis chinensis and berberine relaxed pre-contracted lower esophageal sphincter tissue, apparently through potassium channels.
- Hu Z, Yang X, Ho PC, et al. Herb-drug interactions: a literature review. Drugs. 2005;65(9):1239-82. PMID 15916450. Literature review of herb-drug interactions, including bleeding with warfarin and other clinically significant combinations.
- Saper RB, Phillips RS, Sehgal A, et al. Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA. 2008;300(8):915-23. PMID 18728265. JAMA study finding detectable lead, mercury or arsenic in about one fifth of Ayurvedic medicines purchased over the Internet.
This page is for general education and is not medical advice. Acupuncture, Ayurvedic medicine and herbal medicine are complementary therapies; they do not replace diagnosis or treatment by your physician. Do not stop or change prescribed treatment without talking to your prescriber. In an emergency call 911.


