




















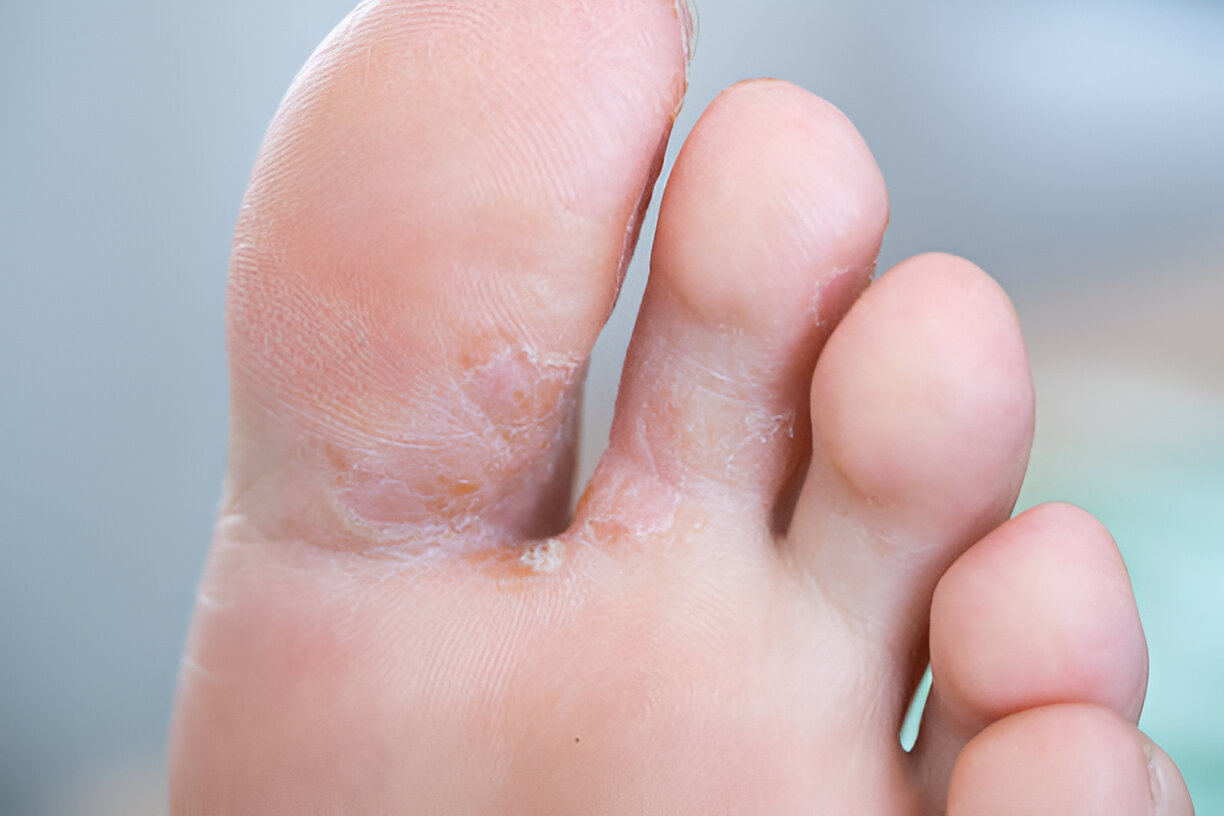
- What it is: A fungal infection of the skin of the feet caused by dermatophyte fungi, usually beginning between the toes.
- Common symptoms: Itchy, scaly, red or cracked skin between the toes, dry scaling on the soles, or sometimes blisters.
- Conventional care: Topical antifungal creams, with oral antifungal medicine for severe or stubborn infections, plus keeping the feet dry.
- How integrative care fits: Herbs, Ayurvedic therapies and acupuncture are used alongside antifungal treatment, not instead of it.
- Evidence at a glance: Limited for herbal medicine, with mixed tea tree oil trials; very limited for acupuncture and Ayurveda, with one moxibustion trial and a case report.
What is Athlete's Foot?
Athlete's foot, or tinea pedis, is a fungal infection of the skin of the feet. It is caused by dermatophytes, mainly Trichophyton rubrum, Trichophyton mentagrophytes and Epidermophyton floccosum.[1] About 3% of the world's population is estimated to have it.[2]
Common symptoms
Athlete's foot usually causes itchy scales and cracks between the toes. Some people have dry scaling and redness along the sides and soles of the feet, and some develop painful blisters.[1] Three main forms are recognized: between the toes (interdigital), dry and thickened (moccasin-type), and blistering (vesiculobullous).[2]
Causes and risk factors
The fungus is picked up from skin contact with the organism, often by walking barefoot in locker rooms, showers and pool areas.[1] Spread within families is common, and it can also pass on contaminated belongings.[2] Wearing closed, non-breathable shoes and having diabetes raise the risk.[1]
The infection can spread to the nails (onychomycosis), hands or other body areas.[1]
How it is diagnosed and treated conventionally
Athlete's foot is often diagnosed from how it looks, but the accuracy of looking alone is low. A skin scraping examined under the microscope can confirm it, and a culture can be sent if needed.[2]
Mild, localized infections usually respond to topical antifungal creams used for one to six weeks. Oral antifungals are kept for severe disease, treatment failure, nail infection or weak immunity.[2] A systematic review of seven trials found that topical terbinafine and butenafine worked better than placebo.[3] Untreated infection can lead to cellulitis, especially in people with diabetes, poor circulation or weakened immunity.[1]
Why Athlete's Foot calls for a whole-person approach
Athlete's foot is a fungal infection, and killing the fungus is the job of antifungal medicine. Other factors decide whether it keeps coming back, and those are where supportive care can fit.
Looking at those factors is a reasonable addition to antifungal treatment, as long as it does not delay or replace it.
Moisture and footwear
Fungi thrive on warm, damp skin. Occlusive shoes raise the risk of infection.[1] Foot care and attention to footwear are part of long-term management.[4]
Shared environments and household contacts
Transmission among family members is the most common route, and contaminated belongings can pass the infection on.[2] Treating the person alone may not be enough if the household keeps being exposed.
Diabetes, circulation and immune health
People with diabetes, weakened immunity or poor circulation in the legs are at higher risk of complications such as cellulitis and bone infection.[1] Anyone in these groups should have athlete's foot treated by a physician.
Recurrence and persistent infection
Infection that persists despite treatment can be a sign that the diagnosis needs to be checked, since clinical diagnosis is not always accurate.[2] Nail infection can also keep reinfecting the skin.[1]
Acupuncture for Athlete's Foot
What the research shows
Research on acupuncture for athlete's foot is very limited. A PubMed search found no sham-controlled acupuncture trials and no systematic reviews for this condition. The closest study is a trial from China of 144 people with tinea pedis who received moxibustion (burning of the herb mugwort over acupuncture points) or a nitramisole cream for 21 days. The moxibustion groups had higher effective rates than the cream group, but this is a single, older trial with a limited abstract.[5]
We found no good evidence that acupuncture itself treats the fungal infection, and it should not be used to replace antifungal medicine.
How acupuncture may work
No studies explain how acupuncture or moxibustion might act on a skin fungus, so we cannot describe a mechanism. Any role for acupuncture would be supportive, for example in stress and general well-being, rather than as treatment for the infection.
What treatment involves
Treatment uses fine, sterile, single-use needles at points chosen for the person, usually left in place for about 20 to 40 minutes. We reassess after a short course of visits. Needling should be avoided through infected, broken or inflamed skin.
Serious problems from acupuncture are rare. In prospective studies, about 9 in 100 patients had a minor reaction such as bleeding, pain or redness at a needle site, and serious events occurred in about 1 in 10,000 patients.[6] Tell the practitioner first if you have a bleeding disorder, take blood thinners, are pregnant, or have a pacemaker (relevant to electroacupuncture). Because infection can spread, people with diabetes or poor circulation in the feet should tell us about any foot sores.
Ayurvedic medicine for Athlete's Foot
The Ayurvedic view
Ayurveda describes ringworm-type fungal infections of the skin as Dadru, a type of Kushta (skin disease) in which Pitta and Kapha are said to dominate.[7] These are traditional categories used to choose treatment, not biomedical diagnoses.
Therapies that may be used
Care is chosen for the individual and traditionally combines:
- Diet and daily routine, such as limiting very sweet, oily and sour foods, and keeping feet clean and dry
- Herbs traditionally used for skin conditions, such as neem and turmeric, applied to the skin or taken by mouth as prescribed
- Herbal washes or pastes for the affected skin
- Panchakarma cleansing procedures, only in selected cases
Panchakarma is not appropriate during pregnancy, acute illness or frailty, and is not a treatment for a fungal infection of the feet.
What the research shows
The research on Ayurveda for athlete's foot is very limited. A PubMed search found no controlled trials. The only clinical report we found was a case report of one man with ringworm of the body (tinea corporis), not athlete's foot, who improved over 42 days of Ayurvedic treatment without recurrence for a month. A single case cannot show that a treatment works.[7]
Herbal medicine for Athlete's Foot
Herbs and formulas that have been studied
The best-studied herbal products for athlete's foot are tea tree oil and ajoene, a compound from garlic, both applied to the skin.[8] A Chinese herbal foot soak has also been compared with an antifungal cream.[9] Herbal preparations applied to the skin may be offered through our transdermal medication therapy.
What the research shows
The evidence is limited and mixed. In a trial of 158 people, a 25% or 50% tea tree oil solution used twice daily for four weeks gave a marked clinical response in about 70% of users, versus 39% on placebo. Cultures were negative in 64% with 50% tea tree oil versus 31% with placebo.[10] An earlier trial of 104 people found that a 10% tea tree oil cream eased symptoms about as well as tolnaftate but was no better than placebo at clearing the fungus on culture.[11]
A small trial in Venezuelan soldiers compared one week of ajoene gel with terbinafine. At 60 days, cultures were negative in 72% of the 0.6% ajoene group, in every patient evaluated in the 1% ajoene group, and in 94% of the terbinafine group, but only 47 of 70 participants were evaluated.[12] In a trial of 100 people from one hospital in China, a herbal foot soak had a higher effective rate and fungal clearance than an antifungal cream, but this was a single-site trial.[9]
A 2025 review concluded that tea tree oil shows modest benefit for tinea pedis, limited by poor blinding and dropouts, and that garlic-derived ajoene shows promise but lacks robust trials.[8]
Safety and herb-drug interactions
Herbs applied to the skin can cause irritation or allergy. In the tea tree oil trial, about 4% of people using it developed moderate to severe dermatitis that cleared after stopping.[10] Broken skin between the toes is more easily irritated, so products should not be used on open or weeping areas without advice.
Herbs taken by mouth can interact with medicines. A literature review described interactions between herbs and prescribed drugs, including bleeding with warfarin.[13] Tell us about every medicine you take, including oral antifungals. In one study, about one fifth of Ayurvedic products bought online contained detectable lead, mercury or arsenic.[14] Herbs should come from tested sources. Tell us if you are pregnant or breastfeeding, or have liver or kidney disease.
Translating traditional medicine into modern biological language
The links drawn here are interpretation, not equivalence. Chinese medicine often describes athlete's foot as damp-heat pouring downward, which is a description of damp, itchy, inflamed skin on the feet. Ayurveda's Kapha and Pitta in Dadru describe moist, red, itchy skin.[7]
In biological terms, the relevant ideas are a warm, moist skin environment that suits dermatophytes, and plant compounds with antifungal activity tested in trials, such as tea tree oil and ajoene.[1, 8] No study has shown that a dosha or a TCM pattern corresponds to a specific biological process.
How this care fits with your medical care
Integrative care for athlete's foot is complementary. See your physician or podiatrist for diagnosis and antifungal treatment, and do not stop or change prescribed medicines without your prescriber. We do not diagnose or treat the fungal infection itself.
Please bring your diagnosis, any skin scraping or culture results, a list of medicines and supplements, and details of antifungal products you have used. Tell us if you have diabetes, circulation problems or a weakened immune system.
When to seek urgent medical care
Untreated athlete's foot can lead to bacterial skin infection, which can become serious, especially with diabetes or poor circulation.[1]
- Redness, warmth, swelling or pain spreading up the foot or leg
- Fever or chills with a foot rash
- Pus, an open sore or a foul-smelling wound on the foot
- Red streaks running up the leg
- Foot infection in someone with diabetes, poor circulation or a weakened immune system
- Rash that does not improve after several weeks of treatment
If you have fever with spreading redness, call 911 or go to the nearest emergency department.
Frequently asked questions
What is athlete’s foot?
Athlete’s foot, or tinea pedis, is a common fungal infection of the skin of the feet, usually starting between the toes. It causes itching, scaling, redness and cracking, and sometimes blisters. It spreads through contact with the fungus on floors, towels, socks and shoes. Antifungal creams usually clear mild cases, and a physician can confirm the diagnosis.
Can acupuncture help with athlete’s foot?
There is very little evidence. We found no sham-controlled acupuncture trials for athlete’s foot. One older trial from China used moxibustion and reported a higher effective rate than a nitramisole cream, but it is a single study. Acupuncture does not kill the fungus and should not replace antifungal treatment.
Does Ayurvedic or herbal medicine work for athlete’s foot?
The evidence is limited. Tea tree oil helped symptoms in trials, but results for clearing the fungus were mixed, and some people developed skin irritation. Garlic-derived ajoene looked promising in a small trial. Ayurveda has only a case report. Herbs are used alongside, not instead of, antifungal medicine.
Can I stop my antifungal medicine if I use herbs or have treatment here?
No. Do not stop or change prescribed medicines without talking to your prescriber. Complementary care does not replace antifungal treatment. If the infection does not improve, spreads, or you have diabetes or poor circulation, see a physician promptly.
How soon might I notice a change?
It differs from person to person and no result can be promised. Antifungal creams are usually used for one to six weeks. Complementary care here is aimed at supporting your overall health and skin care, and we reassess after a short course of visits.
Does insurance cover acupuncture for athlete’s foot?
It may depend on your plan. Netra Integrative Health Clinic accepts most major insurance plans that include out-of-network acupuncture benefits, for example Aetna, Blue Cross Blue Shield, Cigna and UnitedHealthcare, and offers a free benefits check. HSA and FSA cards and CareCredit are also accepted. Call (908) 402-7301 to ask about your plan.
References
- Nigam PK, Syed HA, Saleh D. Tinea Pedis. StatPearls [Internet]. 2023. PMID 29262247. StatPearls chapter on tinea pedis covering causes, symptoms, risk factors, complications such as cellulitis and the role of the healthcare team.
- Leung AK, Barankin B, Lam JM, et al. Tinea pedis: an updated review. Drugs Context. 2023;12. PMID 37415917. Updated review of tinea pedis covering prevalence, transmission, clinical forms, diagnosis and topical and oral antifungal treatment.
- Ward H, Parkes N, Smith C, et al. Consensus for the Treatment of Tinea Pedis: A Systematic Review of Randomised Controlled Trials. J Fungi (Basel). 2022;8(4). PMID 35448582. Systematic review of seven trials (1,042 participants) finding topical terbinafine and butenafine more effective than placebo for tinea pedis.
- Nowicka D, Nawrot U. Tinea pedis-An embarrassing problem for health and beauty-A narrative review. Mycoses. 2021;64(10):1140-1150. PMID 34145648. Narrative review of tinea pedis covering causes, epidemiology, diagnosis, treatment, skin care and prevention.
- Tian YS, Chen L, Ren ZW, et al. [Observation on therapeutic effect of medicinal moxa stick moxibustion for treatment of tinea pedis]. Zhongguo Zhen Jiu. 2009;29(7):537-40. PMID 19835120. Chinese randomized trial of 144 people with tinea pedis finding higher effective rates with moxibustion than with a nitramisole cream.
- Bäumler P, Zhang W, Stübinger T, et al. Acupuncture-related adverse events: systematic review and meta-analyses of prospective clinical studies. BMJ Open. 2021;11(9):e045961. PMID 34489268. Systematic review of 21 prospective studies finding minor acupuncture reactions in about 9 percent of patients and serious events in about 1 per 10,000.
- Singh NK, Sengar AS, Khuntia BB, et al. Successful Ayurvedic Management of Dermatophytosis-A case report. J Ayurveda Integr Med. 2022;13(1):100491. PMID 34961687. Case report of one man with tinea corporis treated with Ayurvedic medicines, describing the Ayurvedic view of ringworm as Dadru Kushta.
- Ufomadu P, Gill BJ, Shimizu I, et al. A Review of The Efficacy of Complementary and Alternative Medicines in Managing Dermatologic Infectious Diseases. J Clin Aesthet Dermatol. 2025;18(12):76-81. PMID 41647766. 2025 review of 17 studies of complementary medicines in skin infections, finding modest benefit of tea tree oil for tinea pedis with methodological limits.
- Li H, Lin J, Chen P, et al. Therapeutic evaluation of herbal foot bath for tinea pedis: Impact on fungal clearance, adverse reactions and patient well-being. Pak J Pharm Sci. 2025;38(2):615-622. PMID 40501260. Randomized trial of 100 people in China comparing a Chinese herbal foot soak with an antifungal cream for tinea pedis.
- Satchell AC, Saurajen A, Bell C, et al. Treatment of interdigital tinea pedis with 25% and 50% tea tree oil solution: a randomized, placebo-controlled, blinded study. Australas J Dermatol. 2002;43(3):175-8. PMID 12121393. Randomized placebo-controlled trial of 158 people finding 25% and 50% tea tree oil improved interdigital tinea pedis more than placebo, with some dermatitis.
- Tong MM, Altman PM, Barnetson RS. Tea tree oil in the treatment of tinea pedis. Australas J Dermatol. 1992;33(3):145-9. PMID 1303075. Randomized trial of 104 people finding 10% tea tree oil cream eased tinea pedis symptoms but did not improve fungal cure over placebo.
- Ledezma E, Marcano K, Jorquera A, et al. Efficacy of ajoene in the treatment of tinea pedis: a double-blind and comparative study with terbinafine. J Am Acad Dermatol. 2000;43(5 Pt 1):829-32. PMID 11050588. Small randomized trial of ajoene from garlic versus terbinafine in tinea pedis in 70 soldiers, with 47 evaluated at 60 days.
- Hu Z, Yang X, Ho PC, et al. Herb-drug interactions: a literature review. Drugs. 2005;65(9):1239-82. PMID 15916450. Literature review of herb-drug interactions including warfarin, St John's wort and others.
- Saper RB, Phillips RS, Sehgal A, et al. Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA. 2008;300(8):915-23. PMID 18728265. JAMA study finding detectable lead, mercury or arsenic in about one fifth of Ayurvedic medicines purchased over the Internet.
This page is for general education and is not medical advice. Acupuncture, Ayurvedic medicine and herbal medicine are complementary therapies; they do not replace diagnosis or treatment by your physician. Do not stop or change prescribed treatment without talking to your prescriber. In an emergency call 911.


