




















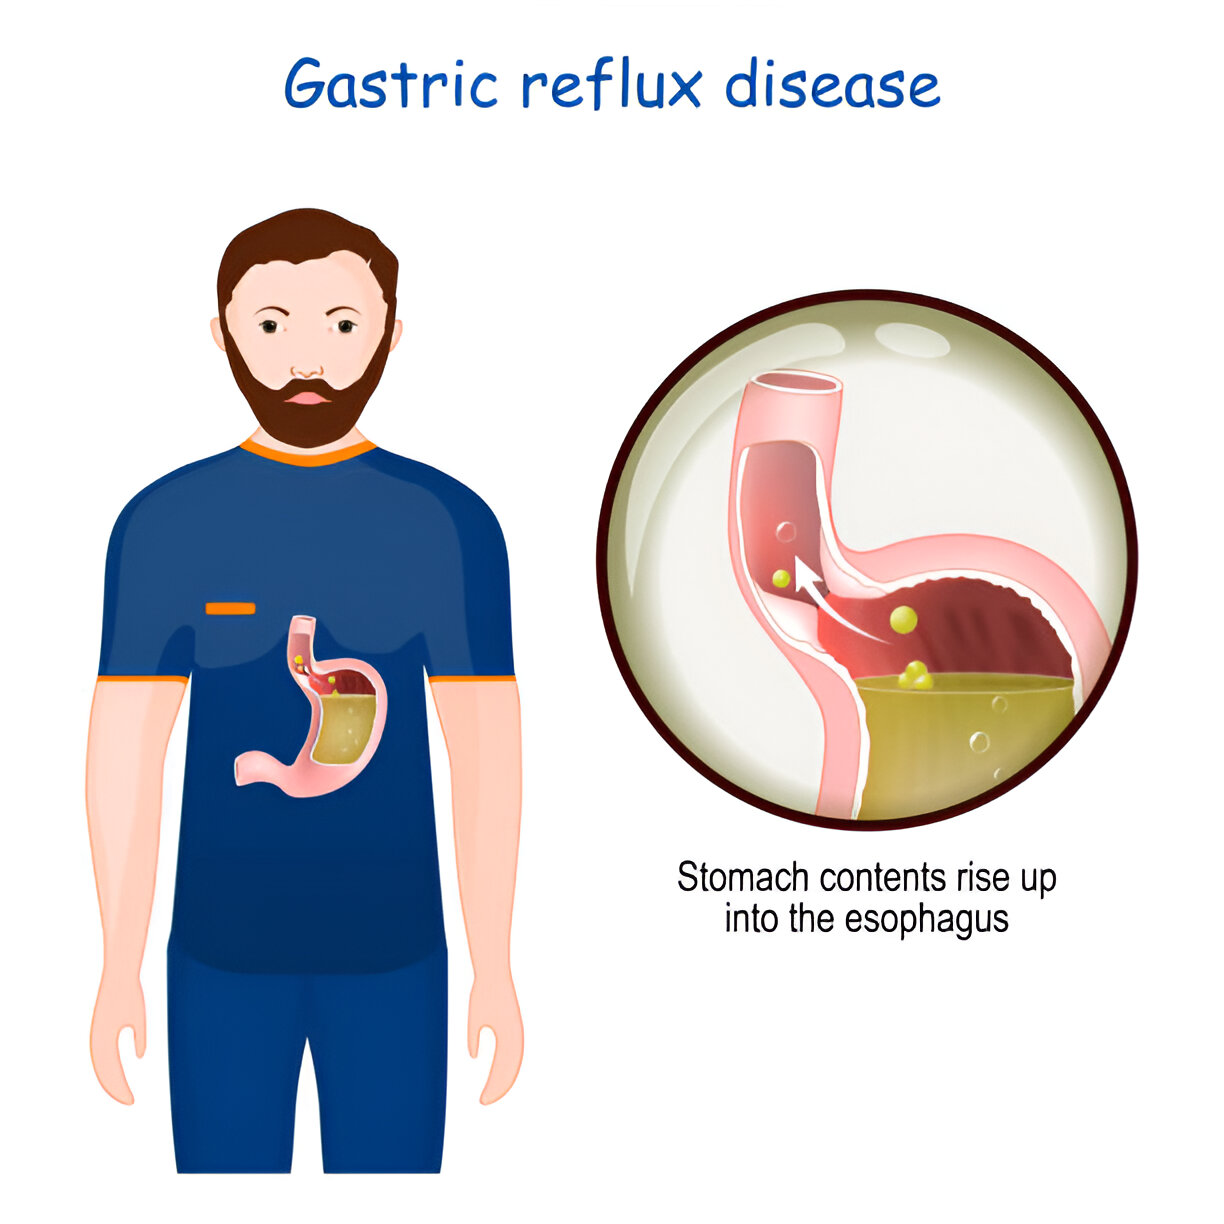
- What it is: A precancerous change in which the normal lining of the lower esophagus is replaced by intestine-like cells, most often after years of acid reflux.
- Common symptoms: Barrett's esophagus itself often causes none; people usually have the heartburn and regurgitation of reflux disease.
- Conventional care: Reflux control with acid-lowering medicine and lifestyle changes, regular endoscopy with biopsies, and endoscopic treatment when dysplasia is found.
- How integrative care fits: Supportive care for reflux symptoms, stress and sleep after the condition is under a gastroenterologist's management.
- Evidence at a glance: None for Barrett's esophagus itself. Studies in reflux disease suggest possible symptom benefit from acupuncture and herbal medicine, but are generally low quality.
What is Barrett's Esophagus?
Barrett's esophagus is a premalignant condition in which the lining of the lower esophagus changes to a type of tissue normally found in the intestine, called intestinal metaplasia. Most cases are acquired, and the usual cause is long-standing gastroesophageal reflux disease (GERD).[1] It is the only known precursor of esophageal adenocarcinoma, a serious cancer, so it is monitored by a physician.[2]
Common symptoms
Barrett's esophagus itself often causes no symptoms. The symptoms people notice come from the reflux that usually accompanies it.[1, 3]
- Heartburn, a burning feeling in the chest
- Regurgitation of sour or bitter fluid into the throat
- Difficulty or pain when swallowing
- Chest pain and, sometimes, a chronic cough
Barrett's esophagus is found in about 5% to 12% of people with chronic reflux symptoms.[1]
Causes and risk factors
Long-standing reflux is the main precipitant.[1] Obesity, tobacco smoking and genetic predisposition raise the risk of reflux disease, which in turn raises the chance of its complications, including Barrett's esophagus.[3] Some families have a rare increased risk through inherited susceptibility.[1] Older age and male sex are also associated with Barrett's esophagus.[1]
How it is diagnosed and treated conventionally
Barrett's esophagus is diagnosed with an upper endoscopy, in which a physician looks at the esophagus with a camera and takes biopsies. The biopsies show whether the cells are intestine-like and whether dysplasia, a precancerous change, is present.[1, 2]
Management is set by the biopsy result. Surveillance endoscopy at intervals your physician chooses is standard, and endoscopic eradication therapy is recommended for high-grade dysplasia and for low-grade dysplasia.[2] A 2024 guideline made a conditional recommendation against eradication therapy in Barrett's esophagus without dysplasia.[4] Reflux is usually controlled with a proton pump inhibitor (PPI) at the lowest effective dose, with weight loss and smoking cessation where relevant.[3]
Why Barrett's Esophagus calls for a whole-person approach
Barrett's esophagus is a medical condition that needs a gastroenterologist. Within that care, the reflux that drives it is influenced by diet, weight, habits, stress and how the digestive tract moves.
Supportive care can address some of these day-to-day factors. It cannot treat the esophageal lining or lower cancer risk, and no study has shown that it does.
Diet and daily habits
A systematic review of 72 studies linked reflux disease to eating late at night, eating quickly, eating beyond fullness, a high-fat diet, smoking and alcohol. Regular exercise was associated with lower risk.[5] The same review found higher intake of vitamins C and E was associated with lower odds of Barrett's esophagus, but these are observational findings.[5]
Weight, smoking and alcohol
Obesity and tobacco smoking raise the risk of reflux disease, and weight loss and smoking cessation are often useful in treatment.[3]
Stress and mood
In the same review, a poor mental state was associated with reflux disease.[5] Stress reduction and sleep are reasonable aims for supportive care, though they are not a treatment for Barrett's esophagus.
Esophageal and gastric movement
Weak esophageal muscle movement and poor stomach emptying can contribute to reflux symptoms.[6] Some acupoint stimulation research focuses on these functions, as described below.
Acupuncture as supportive care in Barrett's Esophagus
What the research shows
No trials of acupuncture in Barrett's esophagus were found, so nothing is known about its effect on the esophageal lining or on cancer risk. What exists is research on reflux disease symptoms, which are the symptoms most people with Barrett's esophagus live with.
A 2017 meta-analysis of 12 trials (1,235 patients) found that adding acupuncture to conventional medicine improved global symptoms more than medicine alone, and that recurrence was lower with acupuncture than with conventional medicine. The authors noted small trials and poor methods.[7] A 2025 trial-sequential meta-analysis of 12 studies found manual acupuncture may lower symptom scores and recurrence, with very low certainty. It also found symptom improvement was higher with PPIs, and the authors did not recommend acupuncture alone as primary treatment for reflux disease.[8]
A 2026 trial of 72 adults whose symptoms persisted on standard-dose omeprazole compared acupuncture added to that dose with a double dose. Both groups improved, with no significant difference in total reflux score. The acupuncture group reported a larger reduction in heartburn, and the double-dose group did better on regurgitation and sleep disturbance.[9]
How acupuncture may work
Researchers propose that acupoint stimulation may act through the vagus nerve to improve how the esophagus and stomach move. In a small sham-controlled trial of 30 people with reflux disease and weak esophageal movement, 4 weeks of transcutaneous electrical acustimulation lowered reflux symptom scores and improved esophageal contractions and stomach accommodation. Vagal activity rose and correlated with lower esophageal sphincter pressure.[6] A network meta-analysis of 33 studies also found acupoint stimulation with traditional Chinese medicine improved lower esophageal sphincter pressure, with methodological limits that call for cautious interpretation.[10] These are early findings in people with reflux, not Barrett's esophagus.
What treatment involves
Treatment uses fine, sterile, single-use needles placed at points on the abdomen, chest, arms and legs, usually left in place for about 20 to 40 minutes, with reassessment after a short course of visits. Treatment is aimed at symptoms and does not replace endoscopic surveillance.
In prospective studies, about 9 in 100 patients had a minor reaction such as bleeding, soreness or redness at a needle site, and serious events occurred in about 1 in 10,000 patients.[11] Tell the practitioner first if you have a bleeding disorder, take blood thinners, are pregnant, or have a pacemaker (relevant to electroacupuncture).
Ayurvedic medicine as supportive care in Barrett's Esophagus
The Ayurvedic view
Ayurveda does not describe Barrett's esophagus. Its closest traditional category for heartburn and sour regurgitation is Amlapitta, described as an imbalance of Pitta, the principle linked to heat and digestion. These are traditional categories, not biomedical diagnoses.
Therapies that may be used
Supportive care is chosen for the individual and traditionally combines:
- Diet and daily routine intended to calm Pitta, such as regular meals, smaller evening meals and avoiding very spicy, sour or fried food
- Stress-reducing practices such as breathing exercises and steady sleep hours
- Herbs prescribed individually by a qualified practitioner
Meal timing and food choices of this kind overlap with the habits linked to reflux in observational research, such as late-night eating and eating quickly.[5]
Panchakarma is not appropriate during pregnancy, acute illness or frailty. Vomiting or purgation therapies in particular are not suitable for people with esophageal disease, so they should not be used for Barrett's esophagus.
What the research shows
No clinical studies of Ayurvedic treatment for Barrett's esophagus were found, so its effect on the condition is unknown. For reflux-type symptoms, the research is of low quality. One single-group study of 30 people with upward-moving Amlapitta (heartburn and sour belching) given individualized herbo-mineral preparations for 28 days reported symptom improvement, but it had no comparison group, so it cannot show the treatment caused the change.[12]
Herbal medicine as supportive care in Barrett's Esophagus
Herbs and formulas that have been studied
No herb or formula has been tested in people with Barrett's esophagus. For reflux disease, Chinese herbal formulas such as Shugan Jieyu capsule and Sanji powder have been compared with or added to conventional medicine,[13] and a deglycyrrhizinated licorice root extract has been tested against placebo.[14] A review of laboratory, animal and some human data describes curcumin, from turmeric, as protective of the esophagus, including in Barrett's esophagus. That does not show it helps people with the condition, and we do not present it as a treatment.[15]
What the research shows
The evidence for reflux symptoms is limited. A 2024 meta-analysis of 34 trials (3,759 patients) found herbal medicine was more effective than conventional therapy for non-erosive reflux disease on several outcomes, but most outcomes were supported by moderate to low-quality evidence.[16] A 2025 network meta-analysis of 19 trials found Chinese herbal medicine added to conventional treatment was associated with better clinical efficacy and fewer recurrences in refractory reflux, and called for higher-quality trials.[13]
In a placebo-controlled trial of 200 people, a licorice root extract with reduced glycyrrhizin was associated with earlier relief of heartburn and regurgitation over 28 days.[14] These reflux results do not tell us how the herbs act in Barrett's esophagus.
Safety and herb-drug interactions
Herbs are active substances and can interact with medicines. Case reports describe bleeding when warfarin was combined with herbs including dang gui (Angelica sinensis), dan shen (Salvia miltiorrhiza), ginger, ginseng and Boswellia.[17] People taking blood thinners need a practitioner's review before using herbs.
Whole licorice contains glycyrrhizin, which can cause electrolyte imbalance, high blood pressure and water retention, which is why the trial above used a form with it reduced.[14] Do not buy licorice products on your own if you have high blood pressure, heart or kidney disease.
In one study, about one fifth of Ayurvedic medicines bought online contained detectable lead, mercury or arsenic.[18] Herbs should come from tested sources and be prescribed individually. Tell us if you are pregnant or breastfeeding, have liver or kidney disease, take a PPI or other prescribed medicine, or have a procedure or endoscopy planned.
Translating traditional medicine into modern biological language
The links drawn here are interpretation, not equivalence. Chinese medicine often describes reflux as rebellious stomach qi, meaning qi that flows upward instead of downward. Researchers study related ideas such as esophageal and gastric movement, lower esophageal sphincter function and vagal nerve activity.[6, 10]
Ayurveda's aggravated Pitta describes heat, sourness and burning. No study has shown that a dosha or a qi pattern corresponds to a specific biological process, and none of these ideas relates to the cellular change in Barrett's esophagus.
How this care fits with your medical care
Complementary care for Barrett's esophagus is supportive only. For a condition like this, we ask that you are under a physician's care for it and that your treating team knows you are receiving complementary care.
Keep your surveillance endoscopies and biopsy follow-up, and do not stop or change your PPI or any other prescribed medicine without your prescriber. Long-term PPI use needs periodic review with your physician, and that decision belongs to them.[3] We do not diagnose or manage Barrett's esophagus.
Please bring your endoscopy and biopsy reports, your medication and supplement list and the date of your next surveillance.
When to seek urgent medical care
New or changing symptoms in someone with Barrett's esophagus need prompt assessment, because difficulty swallowing, weight loss and bleeding are warning symptoms of esophageal cancer.[3]
- New or worsening difficulty swallowing, or food sticking in the chest
- Unplanned weight loss
- Vomiting blood, or black or bloody stools
- Pain when swallowing, or persistent vomiting
- Chest pain, especially with sweating, shortness of breath or pain spreading to the arm or jaw
- Heartburn that is new in pattern or no longer controlled by your medicine
If any of these occur, call 911 or go to the nearest emergency department.
Frequently asked questions
What is Barrett’s esophagus?
Barrett’s esophagus is a change in the lining of the lower esophagus, usually caused by years of acid reflux, in which the normal lining is replaced by intestine-like cells. It often causes no symptoms of its own. It slightly raises the risk of esophageal cancer, so it needs regular medical follow-up with endoscopy.
Can acupuncture help people with Barrett’s esophagus?
There are no studies in Barrett’s esophagus itself, so acupuncture cannot be said to help the condition. In reflux disease, some trials suggest acupuncture may ease heartburn and other symptoms, but most are small or low quality. It is used only as supportive care alongside your gastroenterologist’s care.
Does Ayurvedic or herbal medicine work for Barrett’s esophagus?
Nobody knows for the condition itself, because no clinical studies were found. Some Chinese herbal formulas and a licorice extract have been studied for reflux symptoms with mixed-quality results. Herbs can interact with medicines such as blood thinners, so they should be prescribed individually and reviewed with your physician.
Can I stop my acid medicine or skip endoscopy if I have acupuncture?
No. Acupuncture, Ayurveda and herbal medicine do not replace acid-lowering medicine, surveillance endoscopy or any treatment your physician recommends. Do not stop or change prescribed medicines without talking to your prescriber, and keep every scheduled follow-up.
How soon might I notice a change in reflux symptoms with acupuncture?
It differs from person to person and no result can be promised. In the 2026 trial, treatment lasted 4 weeks. We reassess after a short course of visits to see whether supportive care is helping your symptoms. It does not change the monitoring you need for Barrett’s esophagus.
Does insurance cover acupuncture for Barrett’s esophagus?
It may. Netra Integrative Health Clinic accepts most major insurance plans that include out-of-network acupuncture benefits, for example Aetna, Blue Cross Blue Shield, Cigna and UnitedHealthcare, and offers a free benefits check. HSA and FSA cards and CareCredit are also accepted. Call (908) 402-7301 to ask about your plan.
References
- Khieu M, Goosenberg E. Barrett Esophagus. StatPearls [Internet]. 2025. PMID 28613697. StatPearls chapter on Barrett esophagus covering definition, link to chronic reflux, prevalence among people with reflux, cancer risk, surveillance and treatment.
- Shaheen NJ, Falk GW, Iyer PG, et al. Diagnosis and Management of Barrett's Esophagus: An Updated ACG Guideline. Am J Gastroenterol. 2022;117(4):559-587. PMID 35354777. American College of Gastroenterology guideline on diagnosing and managing Barrett's esophagus, including surveillance and endoscopic eradication for dysplasia.
- Maret-Ouda J, Markar SR, Lagergren J. Gastroesophageal Reflux Disease: A Review. JAMA. 2020;324(24):2536-2547. PMID 33351048. JAMA review of gastroesophageal reflux disease covering risk factors, symptoms, diagnosis, PPI treatment, warning symptoms and lifestyle measures.
- Rubenstein JH, Sawas T, Wani S, et al. AGA Clinical Practice Guideline on Endoscopic Eradication Therapy of Barrett's Esophagus and Related Neoplasia. Gastroenterology. 2024;166(6):1020-1055. PMID 38763697. AGA guideline on endoscopic eradication therapy, strongly recommending it for high-grade dysplasia and conditionally against it in Barrett's without dysplasia.
- Zhang M, Hou ZK, Huang ZB, et al. Dietary and Lifestyle Factors Related to Gastroesophageal Reflux Disease: A Systematic Review. Ther Clin Risk Manag. 2021;17:305-323. PMID 33883899. Systematic review of 72 studies on dietary and lifestyle factors in reflux disease, with associations for meal habits, smoking, alcohol, exercise, mental state and antioxidants in Barrett's.
- Zhang B, Hu Y, Shi X, et al. Integrative Effects and Vagal Mechanisms of Transcutaneous Electrical Acustimulation on Gastroesophageal Motility in Patients With Gastroesophageal Reflux Disease. Am J Gastroenterol. 2021;116(7):1495-1505. PMID 34183577. Sham-controlled trial of 30 people with reflux disease finding transcutaneous electrical acustimulation lowered symptoms and improved esophageal and gastric function through vagal activity.
- Zhu J, Guo Y, Liu S, et al. Acupuncture for the treatment of gastro-oesophageal reflux disease: a systematic review and meta-analysis. Acupunct Med. 2017;35(5):316-323. PMID 28689187. Meta-analysis of 12 trials (1,235 patients) of acupuncture for reflux disease, finding added symptom benefit and lower recurrence, limited by small, poor-quality trials.
- Yin J, Yin M, Liu T, et al. Does Manual Acupuncture Improve Gastroesophageal Reflux Disease Symptoms? A Trial Sequential Meta-Analysis. Complement Med Res. 2025;32(3):233-243. PMID 40127634. 2025 trial sequential meta-analysis of manual acupuncture for reflux disease, with very low certainty benefit and no recommendation for acupuncture alone over PPIs.
- Ghadiani Z, Gorjizadeh N, Azadvari M, et al. Acupuncture provides a safe strategy to minimize proton pump inhibitor dose in resistant gastroesophageal reflux disease: randomized controlled trial. Dis Esophagus. 2026;39(1). PMID 41609334. 2026 trial of 72 adults with PPI-resistant reflux comparing acupuncture plus standard PPI with double-dose PPI, with comparable total symptom reduction.
- Huang M, Yu Z, Wu L, et al. Efficacy of Nonpharmacological Interventions and Combination With Pharmacological Interventions for Gastroesophageal Reflux Disease: A Systematic Review and Network Meta-Analysis. J Clin Gastroenterol. 2025;59(10):943-953. PMID 40838809. Network meta-analysis of 33 nonpharmacological reflux treatments finding acupoint stimulation with Chinese medicine improved lower esophageal sphincter pressure, with methodological limits.
- Bäumler P, Zhang W, Stübinger T, et al. Acupuncture-related adverse events: systematic review and meta-analyses of prospective clinical studies. BMJ Open. 2021;11(9):e045961. PMID 34489268. Systematic review of 21 prospective studies finding minor acupuncture reactions in about 9 percent of patients and serious events in about 1 per 10,000.
- Meenakshi K, Vinteshwari N, Minaxi J, et al. Effectiveness of Ayurveda treatment in Urdhwaga Amlapitta: A clinical evaluation. J Ayurveda Integr Med. 2021;12(1):87-92. PMID 33546994. Single-group study of 30 people with Amlapitta given individualized Ayurvedic preparations for 28 days, reporting symptom improvement without a control group.
- Zhang R, Yang Z, Pan X, et al. The positive role of Chinese herbal medicine as an adjunctive therapy for refractory gastroesophageal reflux disease: A systematic review and network meta-analysis. Medicine (Baltimore). 2025;104(21):e42565. PMID 40419902. Network meta-analysis of 19 trials of Chinese herbal medicine added to standard treatment for refractory reflux, with no serious adverse events and a call for better trials.
- Raj JP, Saxena U, Belhekar MN, et al. Efficacy and Safety of GutGard® in Managing Gastroesophageal Reflux-Related Symptoms: A Phase III, Single-Centre, Double-Blind, Randomized Placebo-Controlled Trial. Complement Med Res. 2025;32(1):26-36. PMID 39929150. Placebo-controlled trial of 200 people finding a licorice root extract with reduced glycyrrhizin brought earlier relief of heartburn and regurgitation.
- Kwiecien S, Magierowski M, Majka J, et al. Curcumin: A Potent Protectant against Esophageal and Gastric Disorders. Int J Mol Sci. 2019;20(6). PMID 30909623. Review of laboratory, animal and some human data on curcumin protection of the esophagus and stomach, including reflux esophagitis and Barrett's esophagus.
- Kim M, Park C, Park JW, et al. Herbal medicine for the treatment of non-erosive reflux disease: A systematic review and meta-analysis. Medicine (Baltimore). 2024;103(45):e40269. PMID 39533605. Meta-analysis of 34 trials (3,759 patients) of herbal medicine for non-erosive reflux disease, with moderate to low-quality evidence of benefit over conventional therapy.
- Milić N, Milosević N, Golocorbin Kon S, et al. Warfarin interactions with medicinal herbs. Nat Prod Commun. 2014;9(8):1211-6. PMID 25233607. Review of reported interactions between warfarin and medicinal herbs, including bleeding events with dang gui, dan shen, ginger, ginseng and Boswellia.
- Saper RB, Phillips RS, Sehgal A, et al. Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA. 2008;300(8):915-23. PMID 18728265. JAMA study finding detectable lead, mercury or arsenic in about one fifth of Ayurvedic medicines purchased over the Internet.
This page is for general education and is not medical advice. Acupuncture, Ayurvedic medicine and herbal medicine are complementary therapies; they do not replace diagnosis or treatment by your physician. Do not stop or change prescribed treatment without talking to your prescriber. In an emergency call 911.


