




















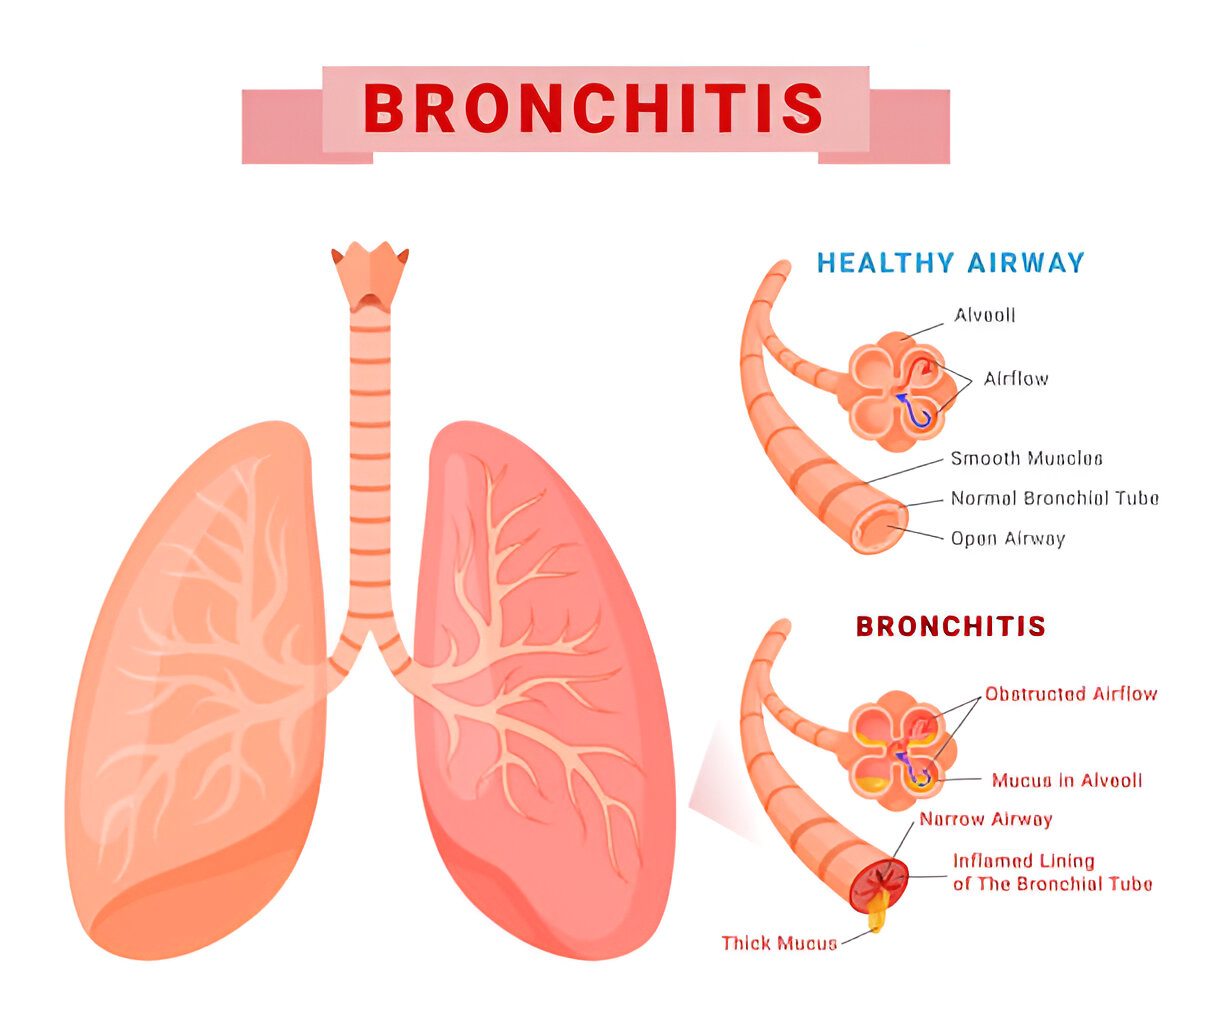
- What it is: Inflammation of the bronchi, either acute (a short illness, usually viral) or chronic (a mucus cough for at least 3 months a year over 2 years).
- Common symptoms: Cough with or without mucus, chest tightness, wheezing, tiredness and sometimes a low-grade fever.
- Conventional care: Acute bronchitis usually settles by itself with symptom relief; chronic bronchitis is managed with smoking cessation, inhalers, rehabilitation and treatment of flare-ups.
- How integrative care fits: Acupuncture, Ayurvedic therapies and individually prescribed herbs are used alongside medical care for cough, comfort, sleep and energy.
- Evidence at a glance: No acupuncture or Ayurveda trials specific to bronchitis were found; limited for herbal medicine, mainly Pelargonium and some Chinese formulas, with low-quality trials.
What is Bronchitis?
Bronchitis is inflammation of the bronchi, the main air passages of the lungs, and it comes in two forms. Acute bronchitis is a short illness with a new cough, with or without sputum, and without pneumonia.[1] Chronic bronchitis is defined as a cough producing sputum for at least 3 months a year over 2 consecutive years.[2]
Common symptoms
The main symptom of both forms is a cough, with or without mucus.[1, 2]
- Wheezing or shortness of breath, especially in chronic bronchitis
- Chest tightness or soreness
- Tiredness
- A sore throat or low-grade fever with acute bronchitis
In chronic bronchitis, the cough is often worse in the morning, and flare-ups tend to follow respiratory infections.[2]
Causes and risk factors
Acute bronchitis is usually triggered by a viral infection, such as a cold or flu.[1] Asthma, COPD, pertussis, COVID-19, influenza and pneumonia can look similar, which is one reason a physician's assessment is useful.[3]
Chronic bronchitis is strongly linked to smoking, but many cases occur in people who never smoked. Dust and fume exposure at work, biomass fuel smoke, childhood asthma and allergies are other known risk factors.[2] Goblet cells in the airway lining overproduce mucus and clear it poorly, which sustains inflammation.[2, 4]
How it is diagnosed and treated conventionally
Acute bronchitis is a clinical diagnosis, and tests are not needed unless a physician suspects another cause such as pneumonia, influenza or COVID-19.[3] It is self-limiting, and cough typically lasts 2 to 3 weeks.[3] Antibiotics shorten the cough by only about half a day and carry side effects, so symptom relief and reassurance are the usual advice.[3] A Cochrane review of 17 trials found limited evidence of clinical benefit from antibiotics in acute bronchitis, with more adverse effects.[5]
Chronic bronchitis is managed by reducing mucus production, improving clearance and limiting inflammation. Smoking cessation is critical, flare-ups are treated with antibiotics, short-acting bronchodilators or oral corticosteroids as needed, and pulmonary rehabilitation helps.[2] Chronic bronchitis can occur with or without COPD, so a physician needs to assess it.[2, 4]
Why Bronchitis calls for a whole-person approach
Bronchitis is often more than a passing airway irritation. Chronic bronchitis is linked to faster lung function decline, more flare-ups and a higher risk of future airflow obstruction.[2, 4]
A broader view looks at the exposures, stress, sleep and overall health that shape recurring symptoms. This view supports medical care and does not replace it.
Irritants and smoke
Smoking is the main cause of chronic bronchitis, and workplace dust, fumes and biomass smoke also contribute.[2] Reducing exposure and quitting smoking are among the most effective steps, and your physician can help with both.
Recurring infections
Respiratory infections trigger acute bronchitis and flare-ups of the chronic form.[1, 2] How well you recover and how often infections return are reasons to look at rest, sleep and general health.
Mucus and inflammation
Excess mucus from goblet cell overgrowth, reduced clearance and airway inflammation lie behind chronic bronchitis.[2, 4] Treatment aims to reduce mucus and support cough mechanics.
Symptoms that wear you down
Persistent cough disturbs sleep and drains energy. Supportive care often aims at these effects of the illness rather than the airway inflammation itself.
Acupuncture for Bronchitis
What the research shows
We found no trials of acupuncture in people with bronchitis. The only item found in PubMed for chronic bronchitis was a protocol for a future review.
Indirect evidence comes from a 2024 meta-analysis of 23 trials across chronic respiratory diseases such as COPD, lung cancer and asthma. It found that acupuncture reduced breathlessness and improved walking distance and quality of life, with no change in FEV1 or FVC. The authors called for larger, higher-quality research.[6] The abstract does not report results for bronchitis separately.
How acupuncture may work
How acupuncture might ease cough or breathlessness is not established, and no mechanism has been shown in bronchitis. Researchers propose effects on the nervous system and inflammatory signaling, but these are proposals and not proof.
What treatment involves
Treatment uses fine, sterile, single-use needles placed at points on the chest, back, arms and legs, usually left in place for about 20 to 40 minutes. A course is typically several visits, and we reassess progress with you during it.
Serious problems are rare. In prospective studies, about 9 in 100 patients had a minor reaction such as brief bleeding, soreness or redness at a needle site, and serious events occurred in about 1 in 10,000 patients.[7] Tell the practitioner first if you have a bleeding disorder, take blood thinners, are pregnant, or have a pacemaker (relevant to electroacupuncture). A fever, worsening cough or breathlessness should be checked by a physician before acupuncture.
Ayurvedic medicine for Bronchitis
The Ayurvedic view
In Ayurveda, a cough with mucus is described as Kasa, and breathing difficulty as Shvasa. These are traditionally linked to excess Kapha, the principle of heaviness and mucus, and to disturbed Vata. These are traditional categories used to choose supportive care, not biomedical diagnoses.
Therapies that may be used
Care is individualized and may include:
- Diet and daily routine that avoid cold, heavy and mucus-producing foods, with warm foods and fluids and regular sleep
- Breathing practices (pranayama) and gentle yoga once an acute illness has passed
- Herbs traditionally used for cough, such as vasaka (Adhatoda vasica), tulsi, pippali and licorice root, prescribed individually
- Warm oil massage of the chest and back, and steam inhalation
Panchakarma procedures are not appropriate during pregnancy, acute illness, fever or frailty. They are not suitable during an acute episode of bronchitis. In chronic bronchitis they should only be considered after discussion with your treating physician. Transdermal medication therapy, in which an herbal preparation is applied to the skin, may also be used; no study we found tests it in bronchitis.
What the research shows
We found no clinical trials of Ayurvedic treatment, Panchakarma or Ayurvedic herbs in people with acute or chronic bronchitis. Reviews of herbs such as Boswellia, curcumin and ashwagandha describe laboratory and general pharmacology findings and not bronchitis trials, so no benefit for bronchitis can be claimed.
Because acute bronchitis usually clears by itself within one to three weeks, improvement after any treatment cannot be credited to that treatment without a comparison group.[1] Supportive routines such as diet, rest and gentle breathing practice have not been shown to change the course of the illness.
Quality matters if herbs are used. About one fifth of Ayurvedic products bought online contained detectable lead, mercury or arsenic, so products should come from tested sources.[8]
Herbal medicine for Bronchitis
Herbs and formulas that have been studied
Several herbal products have been studied for acute bronchitis. They include the Western herb Pelargonium sidoides, ivy leaf extract and Chinese herbal formulas.[9, 10, 11] Herbal patches applied to acupuncture points, a traditional East Asian approach, have also been tested.[12] For chronic bronchitis, one trial tested a Chinese herbal granule formula.[13]
What the research shows
The evidence is limited and mostly low in quality. A meta-analysis of four placebo-controlled trials of a Pelargonium sidoides extract found lower symptom scores by day 7 in acute bronchitis. That review was published in 2008.[9] A Cochrane review rated the evidence as low quality and noted that adverse events were more common with the herb, though none were serious. It also noted doubt and possible publication bias.[14] Ivy leaf extract showed minimal effects of uncertain clinical importance, with low-quality reporting and high risk of bias.[10]
A Cochrane review of Chinese herbs for acute bronchitis found 74 studies reported as randomized trials, but none met the review's standards. It concluded there was insufficient quality data to recommend routine use and that the safety of the herbs was unknown.[11]
For chronic bronchitis, a 2025 multicenter trial of 300 patients in China found that a Chinese herbal granule formula reduced the frequency and severity of flare-ups compared with patient education alone, and cough, sputum and wheezing scores improved. Lung function did not change.[13] The comparison group received education only and no placebo, so the result may be affected by expectation. A review of acupoint herbal patching for bronchitis included 7 trials, all from China with high risk of bias, and reported better treatment response than conventional drug therapy alone, with the authors calling for better-designed trials.[12]
Safety and herb-drug interactions
Herbs are active substances and can interact with medicines. A review of case reports describes serious bleeding or clotting problems when warfarin was combined with herbs including dang gui (Angelica sinensis), dan shen, ginger, ginseng and Boswellia.[15] A broader review found that St John's wort lowered blood levels of theophylline and ciclosporin and that piperine from black and long pepper raised theophylline levels.[16] Tell us about all your medicines, including inhalers, steroids and antibiotics.
In one study, about one fifth of Ayurvedic products bought online contained detectable lead, mercury or arsenic.[8] Herbal and dietary supplements are also a recognized cause of liver injury.[17] Herbs should come from tested sources and be prescribed individually. Tell us if you are pregnant or breastfeeding, have liver or kidney disease, or have surgery planned.
Translating traditional medicine into modern biological language
The links drawn here are interpretation, not equivalence. Chinese medicine often describes cough with mucus as phlegm accumulating in the lung, with patterns labeled wind-cold, wind-heat or phlegm-heat depending on symptoms. Researchers might loosely compare phlegm to airway mucus overproduction and heat to inflammation, which are central ideas in chronic bronchitis research.[2]
Ayurveda's Kapha similarly describes heaviness and mucus. No study has shown that a TCM pattern or a dosha corresponds to a specific biological process in bronchitis.
How this care fits with your medical care
Integrative care for bronchitis is complementary. A cough that lasts more than a few weeks, or a mucus cough that keeps returning, needs a physician's evaluation, because other conditions such as asthma, COPD and pneumonia can look alike.[3]
For chronic bronchitis, we ask that you are under a physician's care for it and that your treating team knows you are receiving complementary care. Do not stop or change prescribed inhalers or other medicines without your prescriber, and do not ask us to replace antibiotics your physician has prescribed. Please bring your diagnosis, spirometry or imaging results, and a full list of medicines and supplements. Chest symptoms in young children belong with a pediatrician.
When to seek urgent medical care
Most acute bronchitis settles on its own, but some symptoms point to pneumonia or another serious problem.[3]
- Severe shortness of breath, or trouble speaking in full sentences
- Blue or gray lips or face
- Coughing up blood
- High or lasting fever, or chest pain with breathing
- Confusion or extreme drowsiness
- A cough lasting more than three weeks, or symptoms that worsen after initially improving
Call 911 or go to the nearest emergency department for any severe symptom.
Frequently asked questions
What is bronchitis?
Bronchitis is inflammation of the bronchial tubes, the airways that carry air into the lungs. Acute bronchitis is a short illness, usually from a virus, with a cough that often lasts 2 to 3 weeks. Chronic bronchitis is a long-term mucus cough lasting at least 3 months a year for two years, most often linked to smoking or irritant exposure.
Can acupuncture help with bronchitis?
We found no trials of acupuncture in people with bronchitis. A pooled analysis of trials in several chronic lung diseases suggested acupuncture may ease breathlessness and improve quality of life without changing lung function, but it does not report bronchitis separately. We offer it as supportive care for comfort, sleep and energy, alongside medical care.
Do Ayurvedic or herbal medicines work for bronchitis?
We found no trials of Ayurvedic treatment in bronchitis. Some herbal products, such as Pelargonium sidoides and a Chinese granule formula for chronic bronchitis, have shown symptom benefits in trials, but the overall evidence is limited and often low quality. A Cochrane review found Chinese herbs for acute bronchitis had insufficient trial quality to recommend. Herbs can interact with medicines.
Can I use this instead of antibiotics or inhalers?
No. Acupuncture, Ayurveda and herbal medicine are complementary care. Do not stop or change prescribed antibiotics, inhalers or other medicines without talking to your prescriber. Most acute bronchitis is viral and needs no antibiotics, but your physician should decide that, especially if you have fever or breathing difficulty.
How soon might I notice a change?
It differs from person to person, and no result can be promised. Acute bronchitis usually improves on its own within a few weeks, so any change in that time may not be due to treatment. For chronic bronchitis, we reassess with you after a short course of visits and keep your physician informed.
Does insurance cover acupuncture for bronchitis?
It may. Netra Integrative Health Clinic accepts most major insurance plans that include out-of-network acupuncture benefits, for example Aetna, Blue Cross Blue Shield, Cigna and UnitedHealthcare, and offers a free benefits check. HSA and FSA cards and CareCredit are also accepted. Call (908) 402-7301 to ask about your plan.
References
- Singh A, Avula A, Zahn E. Acute Bronchitis. StatPearls [Internet]. 2024. PMID 28846312. StatPearls chapter on acute bronchitis describing it as self-limiting bronchial inflammation without pneumonia, usually viral, with cough resolving in 1 to 3 weeks.
- Widysanto A, Goldin J, Mathew G. Chronic Bronchitis. StatPearls [Internet]. 2025. PMID 29494044. StatPearls chapter on chronic bronchitis covering the definition, mucus overproduction, smoking and occupational causes, and management including cessation, rehabilitation and flare-up treatment.
- Mulhem E, Patalinghug E, Eraqi H. Acute Bronchitis: Rapid Evidence Review. Am Fam Physician. 2025;111(3):214-217. PMID 40106287. American Family Physician evidence review of acute bronchitis covering diagnosis, differential diagnosis, expected 2 to 3 week course, and limited benefit of antibiotics.
- Kim V, Criner GJ. Chronic bronchitis and chronic obstructive pulmonary disease. Am J Respir Crit Care Med. 2013;187(3):228-37. PMID 23204254. Review of chronic bronchitis in COPD describing goblet cell mucus overproduction, accelerated lung function decline, more exacerbations and limited treatment options.
- Smith SM, Fahey T, Smucny J, et al. Antibiotics for acute bronchitis. Cochrane Database Syst Rev. 2017;6(6):CD000245. PMID 28626858. Cochrane review of 17 trials (5,099 people) finding limited evidence of benefit from antibiotics in acute bronchitis, with more adverse effects.
- Yu Y, Xiao W, Du LY, et al. Acupuncture for dyspnea and breathing physiology in chronic respiratory diseases: A systematic review and meta-analysis of randomized controlled trials. Heliyon. 2024;10(10):e31176. PMID 38813170. Meta-analysis of 23 trials of acupuncture for breathlessness across chronic respiratory diseases such as COPD, lung cancer and asthma, finding less breathlessness and better quality of life but no change in FEV1 or FVC.
- Bäumler P, Zhang W, Stübinger T, et al. Acupuncture-related adverse events: systematic review and meta-analyses of prospective clinical studies. BMJ Open. 2021;11(9):e045961. PMID 34489268. Systematic review of 21 prospective studies finding minor acupuncture reactions in about 9 percent of patients and serious events in about 1 per 10,000.
- Saper RB, Phillips RS, Sehgal A, et al. Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA. 2008;300(8):915-23. PMID 18728265. JAMA study finding detectable lead, mercury or arsenic in about one fifth of Ayurvedic medicines purchased over the Internet.
- Agbabiaka TB, Guo R, Ernst E. Pelargonium sidoides for acute bronchitis: a systematic review and meta-analysis. Phytomedicine. 2008;15(5):378-85. PMID 18222667. Meta-analysis of six trials of a Pelargonium sidoides extract finding lower symptom scores by day 7 in acute bronchitis, with no serious adverse events.
- Sierocinski E, Holzinger F, Chenot JF. Ivy leaf (Hedera helix) for acute upper respiratory tract infections: an updated systematic review. Eur J Clin Pharmacol. 2021;77(8):1113-1122. PMID 33523253. Systematic review of ivy leaf extract for cough in acute respiratory infections and bronchitis, finding minimal, clinically uncertain effects and low-quality reporting.
- Jiang L, Li K, Wu T. Chinese medicinal herbs for acute bronchitis. Cochrane Database Syst Rev. 2012;2012(2):CD004560. PMID 22336804. Cochrane review finding no Chinese herb trials for acute bronchitis met quality standards and insufficient data to recommend use or confirm safety.
- Jun JH, Kim KH, Song E, et al. Acupoint herbal patching for bronchitis: A systematic review and meta-analysis. Medicine (Baltimore). 2022;101(26):e29843. PMID 35777047. Meta-analysis of seven Chinese trials of acupoint herbal patching for bronchitis showing better response, with high risk of bias and few trials.
- Li D, Shang X, Hong E, et al. Efficacy and Safety of Guben Kechuan Granules in the Treatment of Chronic Bronchitis: A Multi-Center and Randomized Controlled Trial. Drug Des Devel Ther. 2025;19:6885-6896. PMID 40822380. Multicenter trial of 300 patients with chronic bronchitis finding a Chinese herbal granule reduced symptoms and flare-ups versus education only, without changing lung function.
- Timmer A, Günther J, Motschall E, et al. Pelargonium sidoides extract for treating acute respiratory tract infections. Cochrane Database Syst Rev. 2013;2013(10):CD006323. PMID 24146345. Cochrane review of Pelargonium sidoides for acute respiratory infections, finding possible symptom benefit in bronchitis but low-quality evidence and suspected publication bias.
- Milić N, Milosević N, Golocorbin Kon S, et al. Warfarin interactions with medicinal herbs. Nat Prod Commun. 2014;9(8):1211-6. PMID 25233607. Review of reported interactions between warfarin and medicinal herbs, including serious bleeding or clotting case reports with dang gui, dan shen, ginger, ginseng and Boswellia.
- Hu Z, Yang X, Ho PC, et al. Herb-drug interactions: a literature review. Drugs. 2005;65(9):1239-82. PMID 15916450. Literature review of herb-drug interactions including St John's wort and piperine effects on theophylline and ciclosporin levels.
- Navarro VJ, Khan I, Björnsson E, et al. Liver injury from herbal and dietary supplements. Hepatology. 2017;65(1):363-373. PMID 27677775. Hepatology review of liver injury from herbal and dietary supplements, which account for about 20 percent of hepatotoxicity cases in the United States.
This page is for general education and is not medical advice. Acupuncture, Ayurvedic medicine and herbal medicine are complementary therapies; they do not replace diagnosis or treatment by your physician. Do not stop or change prescribed treatment without talking to your prescriber. In an emergency call 911.


