




















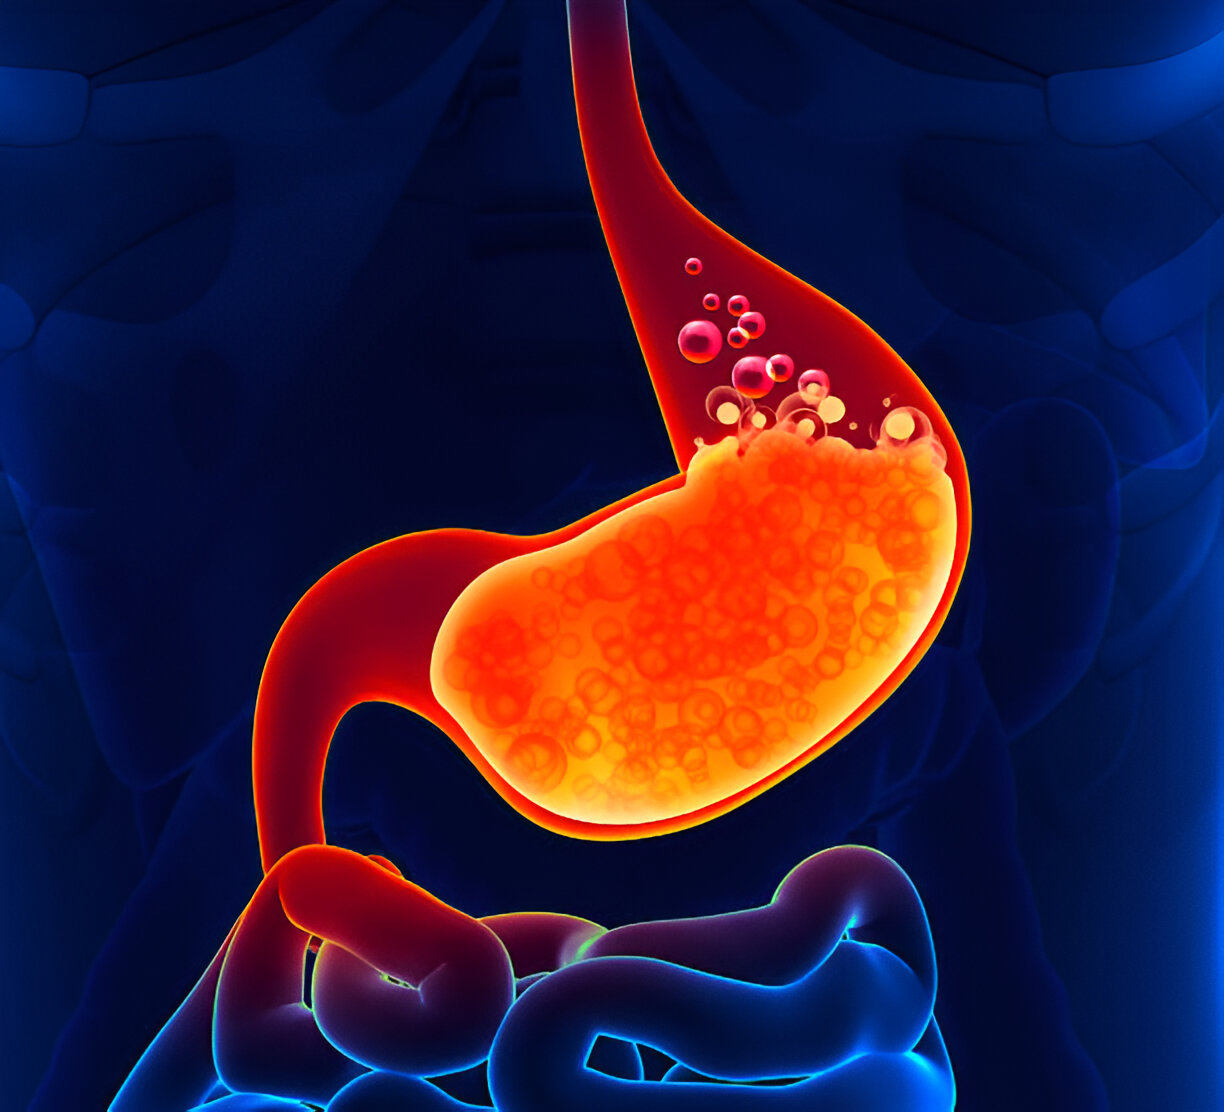
- What it is: A chronic condition in which stomach contents move back up into the esophagus, causing symptoms or damage to its lining.
- Common symptoms: Heartburn, regurgitation, chest pain not caused by the heart, and sometimes cough, hoarseness or trouble swallowing.
- Conventional care: Lifestyle changes, acid-reducing medicines such as proton pump inhibitors, and surgical or endoscopic procedures for selected patients.
- How integrative care fits: Acupuncture, Ayurvedic care and individually prescribed herbs are used alongside medical care to help with reflux symptoms.
- Evidence at a glance: Limited for acupuncture and for Chinese herbal medicine, with small, mostly Chinese trials of variable quality; very limited for Ayurveda.
What is GERD?
GERD is a condition in which stomach contents flow back into the esophagus, the tube from the mouth to the stomach, causing troublesome symptoms or damage to its lining. It is among the most common conditions seen by primary care physicians and gastroenterologists.[1, 2] The lower esophageal sphincter, a ring of muscle at the bottom of the esophagus, normally acts as a valve, and GERD is linked to this valve letting acid and other contents through too often.[1]
Common symptoms
The most common symptoms are heartburn, regurgitation and chest pain that does not come from the heart.[1] Some people also have a sore throat, hoarseness, chronic cough or asthma-like symptoms, and trouble swallowing can occur.[3] Chest pain should always be checked by a physician first, because it can have other causes.
Causes and risk factors
GERD has several contributing causes rather than a single one. In a meta-analysis of studies from many countries, reflux symptoms were more common in people aged 50 or over, smokers, users of aspirin or other NSAID pain relievers, and people with obesity, although the associations were modest.[4] A hiatal hernia and pregnancy can also contribute.[1]
How it is diagnosed and treated conventionally
Typical symptoms are often enough for a physician to make the diagnosis, and a trial of a proton pump inhibitor (PPI) is commonly used. Endoscopy, esophageal manometry and pH monitoring are used when symptoms are unclear, do not respond to treatment, or come with warning signs such as trouble swallowing, bleeding or weight loss.[1, 3]
Treatment includes lifestyle changes, medicines and, in selected people, surgery. Weight loss and quitting smoking help when they apply. Avoiding late evening meals and raising the head of the bed reduce nighttime acid exposure.[5] PPIs remain the main medical treatment, and long-term use needs periodic review by the prescriber.[2, 3]
Why GERD calls for a whole-person approach
Reflux is more than a plumbing problem at the lower esophageal sphincter. Weight, meal timing, stress, mood and how the stomach and esophagus move all play a role, and symptoms can persist in some people despite standard-dose PPIs.[6]
Complementary care aims at some of these other factors. It sits next to, not in place of, acid-reducing treatment and medical follow-up.
Lifestyle, weight and meal timing
Lifestyle is the best-supported area of self-care. Trials and cohort data support weight loss in people who are overweight, stopping smoking, and avoiding late meals.[5] Our Ayurvedic and dietary guidance for reflux follows these medical measures and does not replace them.
Stress, mood and the nervous system
A meta-analysis of 36 studies found that anxiety and depressive symptoms were far more common in people with GERD than in healthy controls, and the relationship appeared to run both ways.[7] This does not mean stress alone causes reflux, but it can make symptoms harder to live with.
Stomach and esophageal movement
Poor esophageal squeezing and impaired stomach function can contribute to reflux. In a small trial of 30 patients, 4 weeks of acupoint electrical stimulation through the skin improved reflux scores, esophageal contractions and stomach relaxation after eating more than sham stimulation, and vagal nerve activity rose during treatment.[8]
Acupuncture for GERD
What the research shows
Acupuncture may help reflux symptoms, but the evidence is limited. A meta-analysis of 12 trials with 1,235 patients found that acupuncture added to Western medicine gave better overall symptom improvement than Western medicine alone, and that recurrence was lower after acupuncture alone than after medication, while global symptom improvement with acupuncture alone was similar to medication. The authors cited small samples and poor methods, and called for better studies.[9]
A 2025 meta-analysis of 12 trials found that manual acupuncture improved symptom scores and reduced recurrence, but it rated the certainty of the evidence as very low or low, and the global symptom improvement rate was lower with acupuncture than with PPIs. Its authors did not recommend manual acupuncture alone as the main treatment for GERD.[10] A network meta-analysis of 33 studies reported that acupoint stimulation combined with Chinese medicine improved pressure in the lower esophageal sphincter and acid exposure, but did not improve quality-of-life scores, and it advised cautious interpretation.[11]
One recent trial of 72 adults with symptoms despite daily PPI treatment compared acupuncture plus a standard PPI dose with a double PPI dose. Both groups improved with no clear difference in total reflux score. Acupuncture was associated with a greater reduction in heartburn and better quality of life, while the double PPI dose did better for regurgitation and sleep disturbance. The authors reported mild, short-lived side effects.[6] This trial had no sham group, so it cannot tell us how much of the improvement is due to needling itself.
How acupuncture may work
Researchers propose that stimulating acupoints, often at the wrist and lower leg, may act through the vagus nerve to improve how the esophagus and stomach move. In a 30-patient sham-controlled trial of electrical stimulation at acupoints, vagal activity rose with treatment and was correlated with lower esophageal sphincter pressure and esophageal contractions.[8] These are proposed mechanisms from small studies, not settled facts.
What treatment involves
Treatment uses fine, sterile, single-use needles at points on the abdomen, wrist and lower leg, usually left in place for about 20 to 40 minutes. Trials have typically run for several weeks, and we reassess after a short course of visits.[6]
Serious problems from acupuncture are rare. In prospective studies, about 9 in 100 patients had a minor reaction such as soreness, bleeding or redness at a needle site, and serious events occurred in about 1 in 10,000 patients.[12] Tell the practitioner first if you have a bleeding disorder, take blood thinners, are pregnant, or have a pacemaker (relevant to electroacupuncture).
Ayurvedic medicine for GERD
The Ayurvedic view
Ayurveda describes acid reflux symptoms as Amlapitta, and the upward-moving form with burning and sour belching as Urdhwaga Amlapitta. It is traditionally seen as an aggravation of Pitta, the principle linked to heat and digestion, often attributed to diet and lifestyle.[13] These are traditional categories, not biomedical diagnoses.
Therapies that may be used
Care is chosen for the individual and traditionally combines:
- Regular, moderate meals, cooling and bland foods, and avoiding very spicy, sour, fried or late meals, which fits the medical advice above[5]
- Daily routine and stress-reducing practices such as slow breathing
- Herbs such as licorice root (Yashtimadhu), used traditionally for Amlapitta and studied in one small clinical trial[14]
- Individually prescribed herbal formulas from tested sources, because some Ayurvedic products contain heavy metals[15]
Panchakarma procedures, especially vomiting or purgation therapies, are not routinely suited to people with reflux. They are not appropriate in pregnancy, acute illness, frailty, or before warning symptoms have been medically assessed.
What the research shows
The research on Ayurveda for GERD itself is very limited. Most studies concern Amlapitta or non-ulcer dyspepsia rather than GERD diagnosed by a physician. A single-arm study of 30 patients given individualized herbo-mineral treatment for 28 days reported symptom relief, but it had no control group.[13] A study of 40 patients compared two licorice-type roots for Amlapitta and found improvement in both groups without a placebo arm.[14] Because the studies are small, uncontrolled or lack a placebo arm, and mostly from one setting, benefit for GERD is uncertain.
Herbal medicine for GERD
Herbs and formulas that have been studied
Most research is on Chinese herbal formulas. These include Jianpi (spleen-strengthening) and Ligan Hewei (liver-soothing, stomach-harmonizing) approaches, and formulas such as Xiangsha Liujunzi decoction and Wu Zhu Yu Tang.[16, 17, 18]
What the research shows
The evidence is limited. A network meta-analysis of 17 trials with 1,441 participants suggested that Jianpi and Ligan Hewei approaches, alone or with PPIs, may be useful complementary treatments, but called for better-designed trials.[16] A meta-analysis of 8 trials of Xiangsha Liujunzi decoction in reflux esophagitis found better outcomes and less recurrence than controls, but rated the evidence as low certainty.[17]
In a double-blind trial of 204 patients with nonerosive reflux disease, a Jianpi Qinghua granule plus a half-dose PPI gave more complete symptom resolution at 4 weeks than a standard PPI dose, though sufficient relief did not differ significantly.[19] In a 90-patient double-blind trial (77 completed), Wu Zhu Yu Tang gave symptom scores similar to omeprazole, and the authors called for larger studies.[18] Nearly all of this work comes from East Asia.
Safety and herb-drug interactions
Herbs can cause side effects. In the Jianpi Qinghua trial, three patients in the herb-plus-PPI group developed liver dysfunction, including two moderate-to-severe cases.[19] Tell us if you have liver or kidney disease, are pregnant or breastfeeding, take blood thinners, or have surgery planned. Herbs should be reviewed against all your medicines, including blood pressure and blood sugar medicines.
Licorice, which is used traditionally for reflux, can raise blood pressure and lower potassium and needs caution in pregnancy.[20] About one fifth of Ayurvedic products bought online contained detectable lead, mercury or arsenic.[15] Herbs should come from tested sources and be prescribed individually.
Translating traditional medicine into modern biological language
This is interpretation, not equivalence. Chinese medicine often describes reflux as stomach qi rising when it should descend, sometimes with liver qi stagnation or spleen weakness. Researchers studying acupuncture look at things that loosely parallel this picture: vagal nerve activity, esophageal and stomach movement and lower esophageal sphincter pressure.[8, 11]
Ayurveda's aggravated Pitta describes heat and burning in the upper digestive tract, along with meals, stress and routine.[13] No study has shown that a dosha corresponds to a specific biological process.
How this care fits with your medical care
Integrative care for GERD is complementary. For a condition like this, we ask that you are under a physician's care for it and that your treating team knows you are receiving complementary care. Do not stop, reduce or change a PPI or other prescribed medicine without your prescriber.
We do not diagnose GERD or manage its complications. Symptoms that are new, frequent or not controlled by medicine should be medically evaluated. Please bring your diagnosis, any endoscopy or pH test results, and a full list of medicines and supplements.
When to seek urgent medical care
Some symptoms point to a complication or a different, more serious problem.[1, 3]
- Chest pain or pressure, especially with shortness of breath, sweating, or pain spreading to the arm or jaw
- Trouble or pain with swallowing, or food that feels stuck
- Vomiting blood, material that looks like coffee grounds, or black or bloody stools
- Persistent vomiting
If you have chest pain with these symptoms or any emergency, call 911 or go to the nearest emergency department. See your physician promptly for unplanned weight loss, symptoms that continue despite medicine, or pale skin and tiredness that may suggest anemia.
Frequently asked questions
What is GERD?
GERD is a long-term condition in which stomach contents flow back into the esophagus, causing heartburn, regurgitation or damage to the esophageal lining. It is common and often diagnosed from typical symptoms. Treatment usually includes lifestyle changes and acid-reducing medicines. Some people need further testing, and long-standing symptoms deserve medical review.
Can acupuncture help with GERD?
It may help some symptoms, but the evidence is limited. Meta-analyses of mostly Chinese trials found better symptom outcomes when acupuncture was added to medicine, but the trials were small and low in quality, and authors do not recommend it as the only treatment. It is used alongside medical care, not in place of it.
Do Ayurvedic or herbal medicines work for GERD?
Evidence is thin. Ayurvedic studies are mainly small studies of Amlapitta or dyspepsia, often without placebo groups. Chinese herbal formulas have been tested in double-blind trials of reflux, with some positive results, but the studies are few and mostly from East Asia. Herbs can cause side effects, including liver problems, and must be reviewed with your medicines.
Can I stop my PPI or other reflux medicine if I try acupuncture or herbs?
No. Acupuncture, Ayurveda and herbal medicine are complementary care. Do not stop, reduce or change a PPI or any prescribed medicine without talking to your prescriber. If you have trouble swallowing, bleeding, weight loss or chest pain, you need prompt medical assessment.
How soon might I notice a change with acupuncture?
It differs from person to person and no result can be promised. In the trials, courses ran for about four weeks of regular sessions. We reassess after a short course of visits to see whether treatment is helping, and we ask you to keep your physician informed.
Does insurance cover acupuncture for GERD?
It may. Netra Integrative Health Clinic accepts most major insurance plans that include out-of-network acupuncture benefits, for example Aetna, Blue Cross Blue Shield, Cigna and UnitedHealthcare, and offers a free benefits check. HSA and FSA cards and CareCredit are also accepted. Call (908) 402-7301 to ask about your plan.
References
- Goosenberg E, Vadakekut ES. Gastroesophageal Reflux Disease (GERD). StatPearls [Internet]. 2025. PMID 32119349. StatPearls chapter on GERD covering definition, symptoms, complications, risk factors, diagnosis based on symptoms and PPI response, and alarm features.
- Katz PO, Dunbar KB, Schnoll-Sussman FH, et al. ACG Clinical Guideline for the Diagnosis and Management of Gastroesophageal Reflux Disease. Am J Gastroenterol. 2022;117(1):27-56. PMID 34807007. American College of Gastroenterology guideline on diagnosis and management of GERD, covering lifestyle, medicines, surgery and the role of PPIs.
- Maret-Ouda J, Markar SR, Lagergren J. Gastroesophageal Reflux Disease: A Review. JAMA. 2020;324(24):2536-2547. PMID 33351048. JAMA review of GERD covering symptoms, risk factors, endoscopy indications, PPI therapy, fundoplication and long-term follow-up.
- Eusebi LH, Ratnakumaran R, Yuan Y, et al. Global prevalence of, and risk factors for, gastro-oesophageal reflux symptoms: a meta-analysis. Gut. 2018;67(3):430-440. PMID 28232473. Meta-analysis of 102 studies of reflux symptoms showing higher prevalence with age 50 or over, smoking, NSAID use and obesity, and wide variation between countries.
- Ness-Jensen E, Hveem K, El-Serag H, et al. Lifestyle Intervention in Gastroesophageal Reflux Disease. Clin Gastroenterol Hepatol. 2016;14(2):175-82.e1-3. PMID 25956834. Systematic review of lifestyle interventions in GERD supporting weight loss, smoking cessation, avoiding late meals and raising the head of the bed.
- Ghadiani Z, Gorjizadeh N, Azadvari M, et al. Acupuncture provides a safe strategy to minimize proton pump inhibitor dose in resistant gastroesophageal reflux disease: randomized controlled trial. Dis Esophagus. 2026;39(1). PMID 41609334. Randomized trial of 72 adults with PPI-resistant GERD comparing acupuncture plus standard PPI dose with double PPI dose, finding similar total reflux scores.
- Zamani M, Alizadeh-Tabari S, Chan WW, et al. Association Between Anxiety/Depression and Gastroesophageal Reflux: A Systematic Review and Meta-Analysis. Am J Gastroenterol. 2023;118(12):2133-2143. PMID 37463429. Meta-analysis of 36 studies finding anxiety and depressive symptoms common in GERD, with evidence of a two-way relationship.
- Zhang B, Hu Y, Shi X, et al. Integrative Effects and Vagal Mechanisms of Transcutaneous Electrical Acustimulation on Gastroesophageal Motility in Patients With Gastroesophageal Reflux Disease. Am J Gastroenterol. 2021;116(7):1495-1505. PMID 34183577. Sham-controlled trial of 30 patients finding acupoint electrical stimulation improved GERD scores, esophageal contractions, gastric accommodation and vagal activity.
- Zhu J, Guo Y, Liu S, et al. Acupuncture for the treatment of gastro-oesophageal reflux disease: a systematic review and meta-analysis. Acupunct Med. 2017;35(5):316-323. PMID 28689187. Meta-analysis of 12 trials (1,235 patients) of acupuncture for GERD finding better global improvement as an add-on and lower recurrence, with poor study quality.
- Yin J, Yin M, Liu T, et al. Does Manual Acupuncture Improve Gastroesophageal Reflux Disease Symptoms? A Trial Sequential Meta-Analysis. Complement Med Res. 2025;32(3):233-243. PMID 40127634. 2025 trial sequential meta-analysis of 12 studies of manual acupuncture for GERD finding lower symptom scores and recurrence with very low-certainty evidence.
- Huang M, Yu Z, Wu L, et al. Efficacy of Nonpharmacological Interventions and Combination With Pharmacological Interventions for Gastroesophageal Reflux Disease: A Systematic Review and Network Meta-Analysis. J Clin Gastroenterol. 2025;59(10):943-953. PMID 40838809. Network meta-analysis of 33 studies of non-drug treatments for GERD, including acupoint stimulation, finding benefit for sphincter pressure but not quality of life.
- Bäumler P, Zhang W, Stübinger T, et al. Acupuncture-related adverse events: systematic review and meta-analyses of prospective clinical studies. BMJ Open. 2021;11(9):e045961. PMID 34489268. Systematic review of 21 prospective studies finding minor acupuncture reactions in about 9 percent of patients and serious events in about 1 per 10,000.
- Meenakshi K, Vinteshwari N, Minaxi J, et al. Effectiveness of Ayurveda treatment in Urdhwaga Amlapitta: A clinical evaluation. J Ayurveda Integr Med. 2021;12(1):87-92. PMID 33546994. Single-arm study of 30 patients with Urdhwaga Amlapitta given individualized Ayurvedic treatment, describing the Ayurvedic concept and reporting symptom relief.
- Prajapati SM, Patel BR. A comparative clinical study of Jethimala (Taverniera nummularia Baker.) and Yashtimadhu (Glycyrrhiza glabra Linn.) in the management of Amlapitta. Ayu. 2015;36(2):157-62. PMID 27011716. Comparison of two licorice-type roots in 40 patients with Amlapitta, with symptom improvement in both and no placebo group.
- Saper RB, Phillips RS, Sehgal A, et al. Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA. 2008;300(8):915-23. PMID 18728265. JAMA study finding detectable lead, mercury or arsenic in about one fifth of Ayurvedic medicines purchased over the Internet.
- Dai YK, Wu YB, Wen H, et al. Different Traditional Herbal Medicines for the Treatment of Gastroesophageal Reflux Disease in Adults. Front Pharmacol. 2020;11:884. PMID 32765255. Network meta-analysis of 17 trials (1,441 participants) of traditional herbal medicines for GERD, favoring Jianpi and Ligan Hewei approaches, with calls for better trials.
- Tian M, Wang K, Chen D. Efficacy and mechanisms of Xiangsha Liujunzi Decoction for gastroesophageal reflux disease: A study integrating meta-analysis, network pharmacology and molecular docking. Phytomedicine. 2026;151:157766. PMID 41506102. Meta-analysis of 8 trials of Xiangsha Liujunzi decoction for reflux esophagitis showing benefit with low-certainty evidence and computer-derived mechanisms.
- Shih YS, Tsai CH, Li TC, et al. Effect of wu chu yu tang on gastroesophageal reflux disease: Randomized, double-blind, placebo-controlled trial. Phytomedicine. 2019;56:118-125. PMID 30668332. Double-blind trial of 90 GERD patients comparing the Chinese formula Wu Zhu Yu Tang with omeprazole, finding similar symptom scores.
- Zhang J, Che H, Zhang B, et al. JianpiQinghua granule reduced PPI dosage in patients with nonerosive reflux disease: A multicenter, randomized, double-blind, double-dummy, noninferiority study. Phytomedicine. 2021;88:153584. PMID 34119741. Double-blind trial of 204 patients with nonerosive reflux disease testing Jianpi Qinghua granules plus half-dose PPI versus PPI alone, with three liver dysfunction cases.
- Nazari S, Rameshrad M, Hosseinzadeh H. Toxicological Effects of Glycyrrhiza glabra (Licorice): A Review. Phytother Res. 2017;31(11):1635-1650. PMID 28833680. Review of the toxicity of licorice (Glycyrrhiza glabra), identifying high blood pressure and low potassium as main adverse effects and caution in pregnancy.
This page is for general education and is not medical advice. Acupuncture, Ayurvedic medicine and herbal medicine are complementary therapies; they do not replace diagnosis or treatment by your physician. Do not stop or change prescribed treatment without talking to your prescriber. In an emergency call 911.


