




















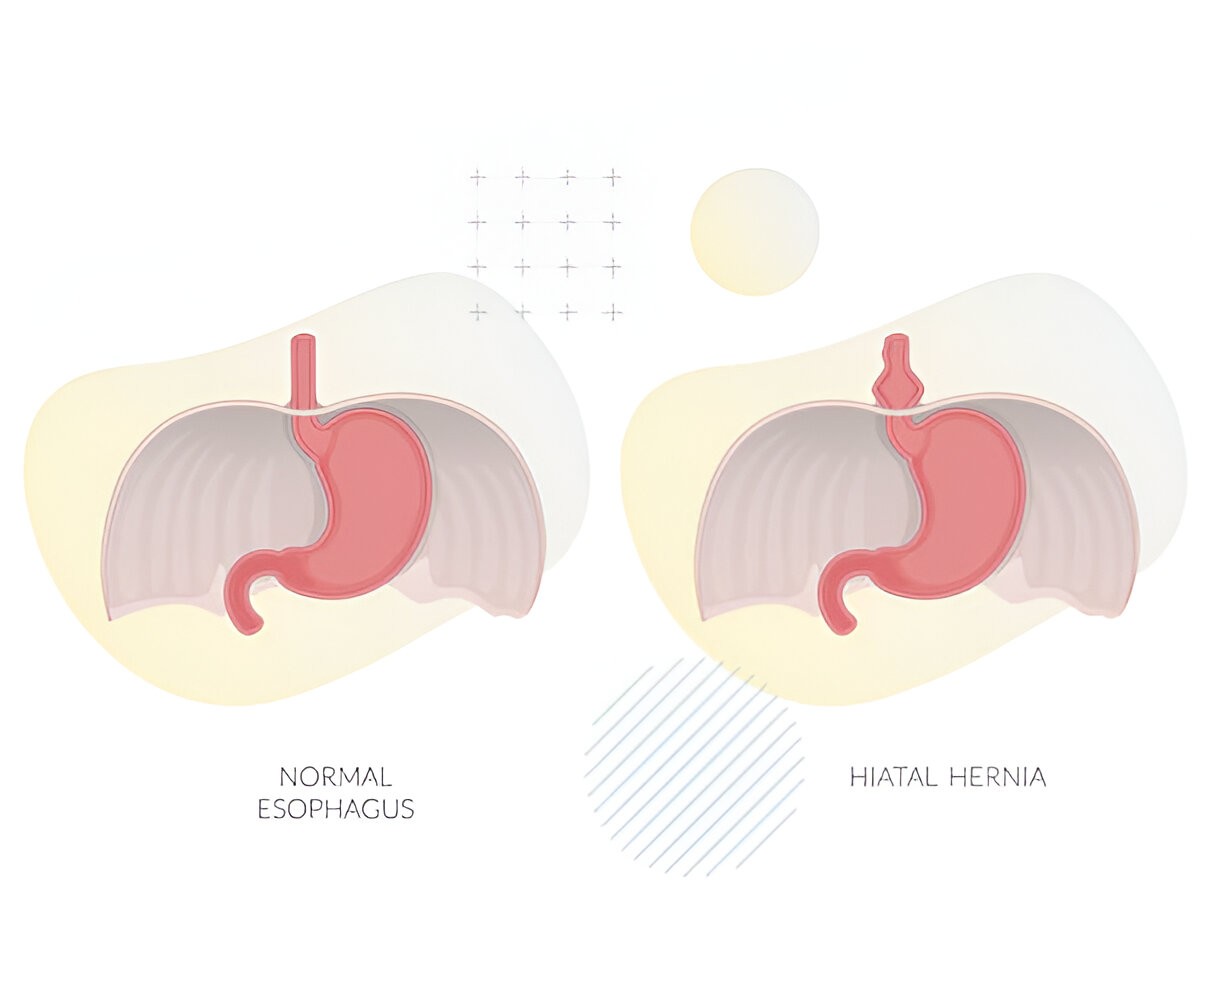
- What it is: A condition in which part of the stomach pushes up through the diaphragm's opening for the esophagus into the chest.
- Common symptoms: Many people have none; others have heartburn, regurgitation, chest discomfort, trouble swallowing or feeling full quickly.
- Conventional care: Observation or reflux medicines for small hernias, and surgical repair for larger or complicated ones.
- How integrative care fits: Supportive care for reflux symptoms and stress after the hernia has been medically assessed and while you stay under your physician's care.
- Evidence at a glance: No studies of acupuncture, Ayurveda or herbs for the hernia itself were found; limited evidence exists for reflux symptoms, which are often linked to it.
What is Hiatal Hernia?
A hiatal hernia is a condition in which the upper part of the stomach pushes up through the opening in the diaphragm, called the hiatus, into the chest.[1] The diaphragm is the main breathing muscle, and the esophagus normally passes through the hiatus on its way to the stomach.[1] A hiatal hernia is a physical change in the body, and acupuncture, herbs or Ayurvedic care cannot repair it.
Common symptoms
Small hiatal hernias often cause no symptoms. When symptoms occur, they include heartburn, regurgitation, difficulty swallowing, chest pain and shortness of breath.[1] Other reported symptoms are nausea, bloating and upper abdominal discomfort.[2] Chest pain can have other causes, including the heart, so it should always be assessed by a physician.
Causes and risk factors
Age and a higher body mass index are key risk factors.[2] The most common type is the sliding hernia, in which the junction of the esophagus and stomach moves up into the chest; in the less common paraesophageal types, part of the stomach moves up into the chest beside the esophagus.[1] Smoking and being overweight are also associated with reflux symptoms in general.[3]
How it is diagnosed and treated conventionally
Hiatal hernias are found with imaging or endoscopy, such as a barium swallow, endoscopy, manometry or CT scanning.[2] Small hernias are often managed with medical treatment, while larger paraesophageal hernias usually need surgery.[1]
Reflux from a hiatal hernia is treated with lifestyle changes and acid-reducing medicines.[2, 4] Surgical repair is often combined with fundoplication, and a systematic review found that the evidence for the best surgical approach is mixed and based on studies with a high risk of bias.[5] Decisions about surgery should be made with your surgeon.
Why Hiatal Hernia calls for a whole-person approach
The hernia itself is a structural problem, but how much it bothers a person depends on reflux, meal habits, weight, stress and how the esophagus and stomach move. Between 50 and 94 percent of people with GERD are reported to have a sliding hiatal hernia, so reflux care and hernia care overlap.[1]
Supportive care can address some of these other factors. It does not change the hernia.
Reflux and the lower esophageal sphincter
A hiatal hernia displaces the lower esophageal sphincter, the valve that normally helps block reflux, and a loose valve lets stomach contents and acid back up.[1]
Meals, weight and sleep position
Weight loss in people who are overweight, quitting smoking, avoiding late evening meals and raising the head of the bed each have support from trials and cohort studies in reflux.[6]
Breathing and the diaphragm
The diaphragm surrounds the lower esophageal sphincter. In a small randomized study of patients with reflux confirmed by acid monitoring, diaphragmatic breathing raised sphincter pressure and reduced reflux events after a meal.[7] This was studied in GERD, not specifically in hiatal hernia, and the trial did not find a difference in total acid exposure compared with sham.[7]
Stress and the brain-gut link
An American Gastroenterological Association expert review advises that people with reflux symptoms learn about weight management, diet, relaxation strategies and the brain-gut relationship.[8]
Acupuncture as supportive care in Hiatal Hernia
What the research shows
We found no clinical trials of acupuncture in people with hiatal hernia. The research is on reflux symptoms in GERD, which is often present with a hernia, and it is limited. A meta-analysis of 12 trials with 1,235 patients found better overall symptom improvement when acupuncture was added to Western medicine, with small samples and poor methods noted by the authors.[9] A 2025 meta-analysis rated its evidence as very low to low certainty and did not recommend manual acupuncture alone as the main treatment for GERD.[10]
A trial of 72 adults whose reflux continued on a daily PPI compared acupuncture plus a standard PPI dose with a double dose of PPI. Total reflux scores did not differ between groups, and there was no sham group.[11] Whether the results apply to people with a large hernia is not known.
How acupuncture may work
Researchers propose that acupoint stimulation may act through the vagus nerve to improve how the esophagus and stomach move. In a small sham-controlled trial of electrical acupoint stimulation, vagal activity rose and was linked to sphincter pressure and esophageal contractions.[12] These are proposed mechanisms in GERD from small studies, not proof of an effect on a hernia.
What treatment involves
Treatment uses fine, sterile, single-use needles at points on the abdomen, wrist and lower leg, usually left in place for about 20 to 40 minutes. A short course of visits, with reassessment along the way, is typical.
Serious problems from acupuncture are rare. In prospective studies, about 9 in 100 patients had a minor reaction such as soreness, bleeding or redness at a needle site, and serious events occurred in about 1 in 10,000 patients.[13] Tell the practitioner first if you have a bleeding disorder, take blood thinners, are pregnant, have recently had surgery, or have a pacemaker (relevant to electroacupuncture).
Ayurvedic medicine as supportive care in Hiatal Hernia
The Ayurvedic view
Ayurveda does not describe a hiatal hernia as such. Reflux and burning after meals are described as Amlapitta, traditionally seen as an aggravation of Pitta, the principle linked to heat and digestion.[14] These are traditional categories, not biomedical diagnoses.
Therapies that may be used
Care is chosen for the individual and traditionally combines:
- Regular, moderate meals with cooling, bland foods and less very spicy, sour, fried or late-evening food, which fits the medical advice above[6]
- Daily routine and relaxation practices such as slow breathing
- Herbs traditionally used for Amlapitta, such as licorice root (Yashtimadhu)[15]
- Individually prescribed formulas from tested sources, since some Ayurvedic products contain heavy metals[16]
Panchakarma procedures, especially vomiting or purgation therapies, are not appropriate for people with a hiatal hernia. They are also not appropriate in pregnancy, acute illness, frailty, or after recent surgery.
What the research shows
We found no clinical studies of Ayurvedic treatment in hiatal hernia. For reflux-type symptoms the evidence is very limited. A single-arm study of 30 patients with Amlapitta reported symptom relief after 28 days of individualized treatment but had no control group.[14] A 40-patient study of two licorice-type roots reported less burning in the chest and throat in both groups, without a placebo arm.[15]
Herbal medicine as supportive care in Hiatal Hernia
Herbs and formulas that have been studied
No herbal formula has been studied for hiatal hernia. Chinese herbal formulas, including Jianpi (spleen-strengthening) and Ligan Hewei (liver-soothing, stomach-harmonizing) approaches, have been studied for GERD.[17]
What the research shows
The evidence for reflux symptoms is limited. A network meta-analysis of 17 trials with 1,441 participants suggested Jianpi and Ligan Hewei approaches, alone or with PPIs, may be useful complementary options, and called for better-designed trials.[17] A double-blind trial in 204 people with nonerosive reflux found more complete symptom resolution with a herbal granule plus half-dose PPI than with a full-dose PPI, although the rate of sufficient relief did not differ significantly.[18] These studies did not include people selected for hiatal hernia.
Safety and herb-drug interactions
In that trial, three people in the herb-plus-PPI group developed liver dysfunction, two of them moderate to severe.[18] Tell us if you have liver or kidney disease, are pregnant or breastfeeding, take blood thinners, or have surgery planned. Herbs should be checked against all your medicines.
About one fifth of Ayurvedic products bought online contained detectable lead, mercury or arsenic.[16] Herbs should come from tested sources and be prescribed individually.
Translating traditional medicine into modern biological language
This is interpretation, not equivalence. Chinese medicine often describes reflux as stomach qi rising when it should descend. Researchers studying acupuncture look at things that loosely parallel this picture: vagal nerve activity, lower esophageal sphincter pressure and esophageal and stomach movement.[12]
Ayurveda's aggravated Pitta describes heat and burning in the upper digestive tract.[14] None of these concepts describes or treats the displaced stomach itself.
How this care fits with your medical care
A hiatal hernia needs medical evaluation, and larger hernias may need surgery. For a condition like this, we ask that you are under a physician's care for it and that your treating team knows you are receiving complementary care. Do not stop or change reflux medicines, or delay a surgical decision, because of anything we offer.
We do not diagnose hernias. Please bring your diagnosis, imaging or endoscopy reports, a list of medicines and supplements, and details of any planned or past surgery.
When to seek urgent medical care
A hernia that becomes trapped or twisted is an emergency, as are signs of bleeding.[1]
- Sudden, severe chest or upper abdominal pain
- Repeated vomiting or retching with nothing coming up
- Inability to swallow food or liquid, or food that gets stuck
- Vomiting blood, material that looks like coffee grounds, or black or bloody stools
- Chest pain with shortness of breath, sweating, or pain spreading to the arm or jaw
If any of these occur, call 911 or go to the nearest emergency department.
Frequently asked questions
What is a hiatal hernia?
A hiatal hernia is a condition in which part of the stomach pushes up through the opening in the diaphragm into the chest. Many people have no symptoms. Others have heartburn, regurgitation, chest discomfort or trouble swallowing. Small hernias are often managed with lifestyle changes and medicine, while larger ones may need surgery.
Can acupuncture help people with hiatal hernia?
No studies have tested acupuncture for hiatal hernia itself, and it cannot repair the hernia. Limited research suggests it may ease reflux symptoms in GERD, which often accompanies a hernia, but the trials are small and low in quality. It is used only as supportive care alongside your physician’s treatment.
Do Ayurvedic or herbal medicines help with hiatal hernia?
We found no clinical studies for hiatal hernia. Ayurvedic studies of reflux-type symptoms are small and lack placebo groups, and Chinese herbal formulas for GERD have limited trial evidence. None of these treat the hernia. Herbs can cause side effects, including liver problems, and must be reviewed with your medicines.
Can I avoid surgery or stop my reflux medicine if I use this care?
No. This care is supportive and does not replace medical evaluation, medicines or surgery. Do not stop or change prescribed medicines, or delay a surgical decision, without your physician. If you have severe pain, repeated vomiting or trouble swallowing, you need emergency assessment.
What should I bring to my first visit?
Bring your diagnosis, any imaging or endoscopy reports, a full list of medicines and supplements, and details of any surgery you have had or are planning. This lets us coordinate our supportive care with your treating physicians.
Does insurance cover acupuncture for hiatal hernia?
It may. Netra Integrative Health Clinic accepts most major insurance plans that include out-of-network acupuncture benefits, for example Aetna, Blue Cross Blue Shield, Cigna and UnitedHealthcare, and offers a free benefits check. HSA and FSA cards and CareCredit are also accepted. Call (908) 402-7301 to ask about your plan.
References
- Puri R, Sharma S. Hiatal Hernia. StatPearls [Internet]. 2026. PMID 32965871. StatPearls chapter on hiatal hernia covering types, anatomy, symptoms, the link with GERD, complications such as incarceration and bleeding, and surgical repair.
- Yu HX, Han CS, Xue JR, et al. Esophageal hiatal hernia: risk, diagnosis and management. Expert Rev Gastroenterol Hepatol. 2018;12(4):319-329. PMID 29451037. Review of esophageal hiatal hernia covering risk factors, symptoms, diagnostic tests and medical and surgical management.
- Eusebi LH, Ratnakumaran R, Yuan Y, et al. Global prevalence of, and risk factors for, gastro-oesophageal reflux symptoms: a meta-analysis. Gut. 2018;67(3):430-440. PMID 28232473. Meta-analysis of 102 studies of reflux symptoms showing higher prevalence with age 50 or over, smoking, NSAID use and obesity.
- Katz PO, Dunbar KB, Schnoll-Sussman FH, et al. ACG Clinical Guideline for the Diagnosis and Management of Gastroesophageal Reflux Disease. Am J Gastroenterol. 2022;117(1):27-56. PMID 34807007. American College of Gastroenterology guideline on diagnosis and management of GERD, covering lifestyle, medicines, surgery and the role of PPIs.
- Hanna NM, Kumar SS, Collings AT, et al. Management of symptomatic, asymptomatic, and recurrent hiatal hernia: a systematic review and meta-analysis. Surg Endosc. 2024;38(6):2917-2938. PMID 38630179. Systematic review and meta-analysis of surgical management of hiatal hernia finding evidence for mesh and fundoplication mixed and high risk of bias.
- Ness-Jensen E, Hveem K, El-Serag H, et al. Lifestyle Intervention in Gastroesophageal Reflux Disease. Clin Gastroenterol Hepatol. 2016;14(2):175-82.e1-3. PMID 25956834. Systematic review of lifestyle interventions in GERD supporting weight loss, smoking cessation, avoiding late meals and raising the head of the bed.
- Halland M, Bharucha AE, Crowell MD, et al. Effects of Diaphragmatic Breathing on the Pathophysiology and Treatment of Upright Gastroesophageal Reflux: A Randomized Controlled Trial. Am J Gastroenterol. 2021;116(1):86-94. PMID 33009052. Randomized trial in patients with pH-proven reflux finding diaphragmatic breathing raised sphincter pressure and reduced postmeal reflux events but not total acid exposure versus sham.
- Yadlapati R, Gyawali CP, Pandolfino JE, et al. AGA Clinical Practice Update on the Personalized Approach to the Evaluation and Management of GERD: Expert Review. Clin Gastroenterol Hepatol. 2022;20(5):984-994.e1. PMID 35123084. AGA expert review on personalized GERD care, advising relaxation strategies, weight management and awareness of the brain-gut axis.
- Zhu J, Guo Y, Liu S, et al. Acupuncture for the treatment of gastro-oesophageal reflux disease: a systematic review and meta-analysis. Acupunct Med. 2017;35(5):316-323. PMID 28689187. Meta-analysis of 12 trials (1,235 patients) of acupuncture for GERD finding better global improvement as an add-on, with poor study quality.
- Yin J, Yin M, Liu T, et al. Does Manual Acupuncture Improve Gastroesophageal Reflux Disease Symptoms? A Trial Sequential Meta-Analysis. Complement Med Res. 2025;32(3):233-243. PMID 40127634. 2025 trial sequential meta-analysis of 12 studies of manual acupuncture for GERD finding lower symptom scores with very low-certainty evidence.
- Ghadiani Z, Gorjizadeh N, Azadvari M, et al. Acupuncture provides a safe strategy to minimize proton pump inhibitor dose in resistant gastroesophageal reflux disease: randomized controlled trial. Dis Esophagus. 2026;39(1). PMID 41609334. Randomized trial of 72 adults with PPI-resistant GERD comparing acupuncture plus standard PPI dose with double PPI dose, finding similar total reflux scores.
- Zhang B, Hu Y, Shi X, et al. Integrative Effects and Vagal Mechanisms of Transcutaneous Electrical Acustimulation on Gastroesophageal Motility in Patients With Gastroesophageal Reflux Disease. Am J Gastroenterol. 2021;116(7):1495-1505. PMID 34183577. Sham-controlled trial of 30 patients finding acupoint electrical stimulation improved GERD scores, esophageal contractions and vagal activity.
- Bäumler P, Zhang W, Stübinger T, et al. Acupuncture-related adverse events: systematic review and meta-analyses of prospective clinical studies. BMJ Open. 2021;11(9):e045961. PMID 34489268. Systematic review of 21 prospective studies finding minor acupuncture reactions in about 9 percent of patients and serious events in about 1 per 10,000.
- Meenakshi K, Vinteshwari N, Minaxi J, et al. Effectiveness of Ayurveda treatment in Urdhwaga Amlapitta: A clinical evaluation. J Ayurveda Integr Med. 2021;12(1):87-92. PMID 33546994. Single-arm study of 30 patients with Urdhwaga Amlapitta given individualized Ayurvedic treatment, describing the Ayurvedic concept and reporting symptom relief.
- Prajapati SM, Patel BR. A comparative clinical study of Jethimala (Taverniera nummularia Baker.) and Yashtimadhu (Glycyrrhiza glabra Linn.) in the management of Amlapitta. Ayu. 2015;36(2):157-62. PMID 27011716. Comparison of two licorice-type roots in 40 patients with Amlapitta, with relief of chest and throat burning in both and no placebo group.
- Saper RB, Phillips RS, Sehgal A, et al. Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA. 2008;300(8):915-23. PMID 18728265. JAMA study finding detectable lead, mercury or arsenic in about one fifth of Ayurvedic medicines purchased over the Internet.
- Dai YK, Wu YB, Wen H, et al. Different Traditional Herbal Medicines for the Treatment of Gastroesophageal Reflux Disease in Adults. Front Pharmacol. 2020;11:884. PMID 32765255. Network meta-analysis of 17 trials (1,441 participants) of traditional herbal medicines for GERD, favoring Jianpi and Ligan Hewei approaches.
- Zhang J, Che H, Zhang B, et al. JianpiQinghua granule reduced PPI dosage in patients with nonerosive reflux disease: A multicenter, randomized, double-blind, double-dummy, noninferiority study. Phytomedicine. 2021;88:153584. PMID 34119741. Double-blind trial of 204 patients with nonerosive reflux disease testing Jianpi Qinghua granules plus half-dose PPI, with three liver dysfunction cases.
This page is for general education and is not medical advice. Acupuncture, Ayurvedic medicine and herbal medicine are complementary therapies; they do not replace diagnosis or treatment by your physician. Do not stop or change prescribed treatment without talking to your prescriber. In an emergency call 911.


