




















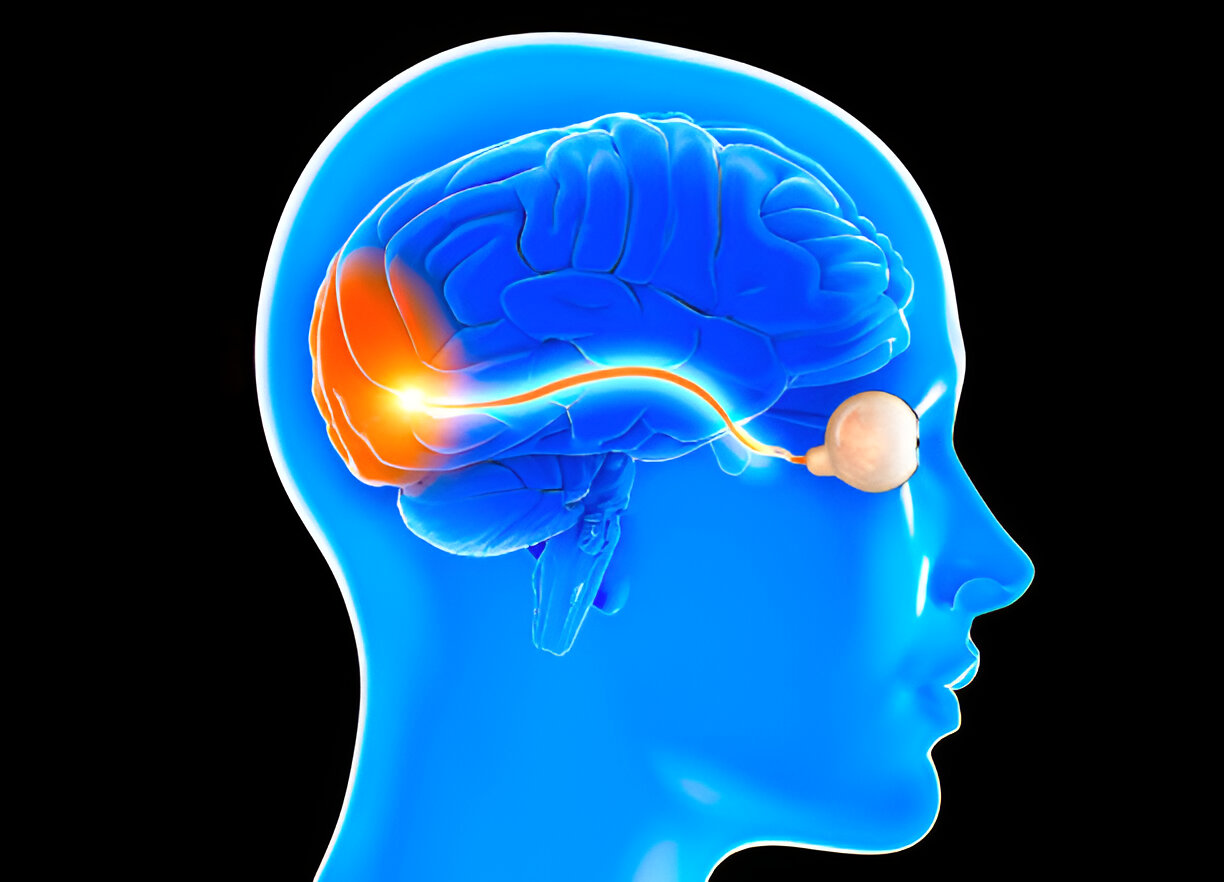
- What it is: Inflammation of the optic nerve that carries visual signals from the eye to the brain, often linked to multiple sclerosis or related autoimmune conditions.
- Common symptoms: Sudden blurred or dim vision in one eye, pain with eye movement, faded colors, and blind spots.
- Conventional care: Urgent eye and neurology evaluation with MRI, usually high-dose corticosteroids, and long-term treatment of any underlying condition.
- How integrative care fits: Supportive care for stress, sleep, fatigue and pain after the condition is under medical management and with your team's knowledge.
- Evidence at a glance: No clinical trials in optic neuritis itself; very limited evidence from related conditions such as optic atrophy and multiple sclerosis.
What is Optic Neuritis?
Optic neuritis is an inflammatory condition of the optic nerve that disrupts the signals sent from the retina to the brain. It causes sudden, sometimes severe vision loss and is most commonly associated with demyelinating diseases, particularly multiple sclerosis (MS) and neuromyelitis optica spectrum disorder (NMOSD).[1] It is a medical emergency for the eye and needs prompt assessment.
Common symptoms
Most people notice sudden vision loss in one eye, ranging from mild blurring to severe loss. Pain, especially with eye movement, is a hallmark and often appears a few days before vision changes.[1]
- Dull or faded colors, especially red
- Reduced contrast sensitivity
- A blind spot or loss of part of the visual field
- Less often, both eyes are affected[1]
Causes and risk factors
Optic neuritis is multifactorial. It is often one of the first signs of MS, and NMOSD is another important autoimmune cause. Infections such as syphilis, Lyme disease, herpes simplex and varicella-zoster, and systemic autoimmune diseases such as lupus and sarcoidosis, can also be responsible. Some cases are idiopathic, and rarely a toxin or drug such as ethambutol or methanol is the trigger.[1]
The cause matters because it affects prognosis and treatment. A related antibody-mediated disorder, MOG antibody-associated disease, is another recognized cause.[2, 3]
How it is diagnosed and treated conventionally
Diagnosis combines an eye examination, visual field testing and MRI of the brain and orbits with contrast, and may include optical coherence tomography, blood antibody tests and sometimes a lumbar puncture.[1]
The mainstay of treatment is a short course of high-dose intravenous corticosteroids, followed in some cases by an oral taper. Steroids speed visual recovery but do not change the long-term visual outcome.[1] In selected cases, plasmapheresis may be used, and long-term immune-modifying therapy may be considered for MS or NMOSD.[1, 2] Most people with typical optic neuritis regain good high-contrast vision, though contrast sensitivity and motion perception may stay reduced, and recovery can be poorer in antibody-mediated forms.[2, 4]
Why Optic Neuritis calls for a whole-person approach
Optic neuritis is a visible sign of an immune process that can involve the brain and spinal cord, so care often reaches beyond the eye. Long-term outlook depends on the underlying cause, and living with vision changes brings its own physical and emotional load.[2, 4]
Supportive care can address some of that load. It does not treat the nerve inflammation.
The underlying immune condition
Optic neuritis may be the first clinical sign of MS, and an accurate diagnosis of the underlying condition guides treatment.[1, 3] This is why specialist follow-up comes first.
Lasting visual effects
Even when sharpness recovers, residual deficits in contrast sensitivity, binocular vision and motion perception may reduce vision-related quality of life.[2]
Fatigue
Fatigue is a common and disabling symptom in MS, one of the main conditions behind optic neuritis.[5]
Stress and sleep
Stress and poor sleep are common companions of a sudden, frightening vision problem, and these are the areas where supportive care is most reasonable. The only related human report is a single case of a long-standing visual field defect, with optic neuritis among the possible diagnoses, in which the authors emphasized chronic stress and used an integrative approach. A single case cannot show cause or benefit.[6]
Acupuncture as supportive care in Optic Neuritis
What the research shows
No clinical trials of acupuncture in optic neuritis were found in PubMed. Acupuncture should never delay or replace urgent eye and neurology care.
The nearest evidence concerns optic atrophy, damage to the optic nerve from various causes. A meta-analysis of nine trials found better visual acuity and visual field results with manual acupuncture than with medication alone, but the authors concluded that serious flaws in study design mean it cannot be said to work better than medicine.[7] That condition is not optic neuritis.
For symptoms around the condition, a meta-analysis of 24 trials suggested acupuncture may improve sleep in insomnia, with benefit appearing after about three weeks.[8] A 2024 meta-analysis of six studies (four randomized trials and two observational studies) found that acupuncture may reduce fatigue and improve quality of life in people with MS, but the authors noted a prevalent risk of bias.[5]
How acupuncture may work
In a mouse model of optic neuritis, needling at one acupoint changed the expression of retinal genes involved in axon growth.[9] This is animal research. It shows a possible biological pathway, not a benefit for people.
What treatment involves
Treatment uses fine, sterile, single-use needles, usually left in place for about 20 to 40 minutes. A short course of visits is followed by reassessment. Needling near the eyes is best avoided unless your eye team agrees, and treatment should wait until your diagnosis and medical treatment are established.
Serious problems from acupuncture are rare. In prospective studies, about 9 in 100 patients had a minor reaction such as brief bleeding, soreness or redness at a needle site, and serious events occurred in about 1 in 10,000 patients.[10] Tell the practitioner first if you have a bleeding disorder, take blood thinners or immune-suppressing medicines, are pregnant, or have a pacemaker (relevant to electroacupuncture).
Ayurvedic medicine as supportive care in Optic Neuritis
The Ayurvedic view
Ayurveda has no classical diagnosis equal to optic neuritis. Eye diseases are traditionally discussed under the eye-related disorders (Netra roga), often linked to imbalance of Pitta. This is a traditional framework, not a biomedical diagnosis.
Therapies that may be used
Once you are under medical care, supportive Ayurvedic care may include:
- Diet and daily routine aimed at steady sleep and digestion
- Gentle stress-reducing practices such as breathing exercises and relaxation
- Individually prescribed herbs, chosen to avoid interactions with your medicines
Panchakarma and eye-focused therapies are not appropriate in the acute phase, during pregnancy, acute illness or frailty, and nothing should be applied to or near the eyes.
What the research shows
There are no clinical trials of Ayurvedic treatment for optic neuritis. In MS, curcumin from turmeric has been studied mostly in the laboratory, where reviews describe anti-inflammatory and immune-regulating effects.[11] A review of curcumin trials in 10 autoimmune diseases found only two trials in MS, with at least one reporting improvement in clinical outcomes, and too little data to pool; the authors called for larger studies.[12] This does not show that curcumin helps optic neuritis.
Herbal medicine as supportive care in Optic Neuritis
Herbs and formulas that have been studied
No herbal trials in optic neuritis were found. In MS, Chinese herbal formulas have been tested alongside conventional treatment in randomized trials.[13]
What the research shows
A 2025 meta-analysis of 28 trials with 1,971 people with MS found that adding Chinese herbal medicine to conventional treatment was associated with lower disability scores, fewer relapses and less fatigue. The authors rated the methods of the trials as suboptimal and called for better studies.[13] These results come from MS and cannot be assumed to apply to optic neuritis.
Safety and herb-drug interactions
Herbs can interact with the medicines used for optic neuritis and MS. Case reports describe herbs such as St John's wort lowering blood levels of immunosuppressants such as ciclosporin and tacrolimus, and other herbs affecting blood clotting.[14] Herbal and dietary supplements account for about one fifth of drug-induced liver injury cases in the United States.[15]
About one fifth of Ayurvedic medicines bought online contained detectable lead, mercury or arsenic.[16] Herbs should come from tested sources and be prescribed individually. Tell us if you are pregnant or breastfeeding, or have liver or kidney disease. Among patients at one inflammatory eye disease clinic, 42% used complementary medicine, and the authors advised physicians to ask about it because of possible interactions with immunosuppressive treatment.[17]
Translating traditional medicine into modern biological language
This is interpretation, not equivalence. Chinese medicine may describe eye and nerve disorders as involving liver and kidney imbalance, heat, or obstruction in the channels. Researchers instead study immune activation, demyelination and nerve fiber injury, and in animals have looked at how needling changes gene expression in the inflamed retina.[9]
Ayurveda's Pitta imbalance describes heat and inflammation in a general way. No study has shown that it corresponds to a specific mechanism in optic neuritis.
How this care fits with your medical care
Optic neuritis needs a physician's care. For a condition like this, we ask that you are under a physician's care for it and that your treating team knows you are receiving complementary care. Our role is limited to supportive care for stress, sleep, fatigue and general well-being, after your condition is under medical management.
Do not stop or change steroids, immune-modifying drugs or any prescribed treatment without your prescriber. We do not diagnose or manage the disease itself. Please bring your diagnosis, MRI and eye examination reports, and a full list of medicines and supplements.
When to seek urgent medical care
Sudden changes in vision need prompt medical evaluation, ideally the same day.
- Sudden loss or blurring of vision in one or both eyes
- Eye pain that worsens with eye movement
- New loss of color vision or a new blind spot
- Worsening vision after an earlier episode, or new vision loss in the other eye
- New weakness, numbness, trouble walking or loss of bladder control, which may signal MS or NMOSD
If any of these occur, call 911 or go to the nearest emergency department.
Frequently asked questions
What is Optic Neuritis?
Optic neuritis is inflammation of the optic nerve, which carries visual signals from the eye to the brain. It causes sudden blurred or dim vision, usually in one eye, often with pain on eye movement and faded colors. It is commonly linked to multiple sclerosis and related conditions and needs urgent medical evaluation.
Can acupuncture help people with Optic Neuritis?
No trials of acupuncture in optic neuritis were found, so we cannot say it helps the condition. Research in related areas is limited and has a high risk of bias. Acupuncture is offered only as supportive care for stress, sleep, fatigue or pain, after your condition is under medical management.
Does Ayurvedic or herbal medicine work for optic neuritis?
There are no trials in optic neuritis. In multiple sclerosis, some small studies of curcumin and a larger group of trials of Chinese herbal formulas reported benefits, but the curcumin studies were few and the herbal trials had weak methods. Herbs can interact with steroids, immune-modifying drugs and blood thinners, so they are used only with your doctors’ knowledge.
Can I use complementary care instead of steroids or other medicine?
No. Optic neuritis needs urgent medical treatment, and complementary care does not replace it. Do not delay seeing an eye doctor or neurologist, and do not stop or change prescribed medicine without your prescriber. Sudden vision loss should be assessed the same day.
How soon might I notice a change?
No result can be promised. Vision often recovers over weeks to months with medical care, so any change after complementary care cannot be credited to it. We reassess after a short course of visits to see whether supportive care is helping with stress, sleep or fatigue.
Does insurance cover acupuncture for optic neuritis?
It may. Netra Integrative Health Clinic accepts most major insurance plans that include out-of-network acupuncture benefits, for example Aetna, Blue Cross Blue Shield, Cigna and UnitedHealthcare, and offers a free benefits check. HSA and FSA cards and CareCredit are also accepted. Call (908) 402-7301 to ask about your plan.
References
- Guier CP, Kaur K, Stokkermans TJ. Optic Neuritis. StatPearls [Internet]. 2025. PMID 32496733. StatPearls chapter on optic neuritis covering causes, symptoms, MRI and OCT diagnosis, high-dose corticosteroid treatment and long-term immunomodulatory therapy.
- Bennett JL, Costello F, Chen JJ, et al. Optic neuritis and autoimmune optic neuropathies: advances in diagnosis and treatment. Lancet Neurol. 2023;22(1):89-100. PMID 36155661. Lancet Neurology review of optic neuritis and autoimmune optic neuropathies: causes, prognosis, residual deficits, and timely steroid and plasmapheresis treatment.
- Petzold A, Fraser CL, Abegg M, et al. Diagnosis and classification of optic neuritis. Lancet Neurol. 2022;21(12):1120-1134. PMID 36179757. Lancet Neurology review proposing diagnostic criteria and classification of optic neuritis, with links to MS, NMOSD and MOG antibody disease.
- Saitakis G, Chwalisz BK. Treatment and Relapse Prevention of Typical and Atypical Optic Neuritis. Int J Mol Sci. 2022;23(17). PMID 36077167. Review of treatment and relapse prevention in typical and atypical optic neuritis, including prognosis and antibody-driven forms.
- Haider S, Fatmi W, Shoaib N, et al. Assessment of acupuncture's effectiveness in mitigating fatigue among patients afflicted with multiple sclerosis: A systematic review and meta-analysis. Complement Ther Clin Pract. 2024;57:101902. PMID 39260078. 2024 meta-analysis of six studies (four trials) finding acupuncture reduced fatigue and improved quality of life in MS, with high risk of bias.
- Kao L, Hui KK, Hui E. A Patient-Centered Integrative Approach Improves Visual Field Defect: A Case Report. Glob Adv Health Med. 2021;10:21649561211021081. PMID 34104579. Single case report of a visual field defect, possibly optic neuritis, improved with an integrative approach including acupuncture; cannot show cause.
- Zhi FY, Liu J, Ma XP, et al. Manual Acupuncture for Optic Atrophy: A Systematic Review and Meta-Analysis. Evid Based Complement Alternat Med. 2019;2019:1735967. PMID 30713567. Meta-analysis of nine trials of manual acupuncture for optic atrophy; benefits shown, but serious methodological flaws prevent firm conclusions.
- Kim SA, Lee SH, Kim JH, et al. Efficacy of Acupuncture for Insomnia: A Systematic Review and Meta-Analysis. Am J Chin Med. 2021;49(5):1135-1150. PMID 34049475. Meta-analysis of 24 trials of acupuncture for insomnia, finding better sleep scores versus drugs, with improvement after about three weeks.
- Chen J, Zhang L, Gan X, et al. Effects of Retinal Transcription Regulation After GB20 Needling Treatment in Retina With Optic Neuritis. Front Integr Neurosci. 2020;14:568449. PMID 33117136. Mouse study of needling at one acupoint in experimental optic neuritis showing changes in retinal gene expression related to axon development.
- Bäumler P, Zhang W, Stübinger T, et al. Acupuncture-related adverse events: systematic review and meta-analyses of prospective clinical studies. BMJ Open. 2021;11(9):e045961. PMID 34489268. Systematic review of 21 prospective studies finding minor acupuncture reactions in about 9 percent of patients and serious events in about 1 per 10,000.
- Yazdani Y, Zamani ARN, Majidi Z, et al. Curcumin and targeting of molecular and metabolic pathways in multiple sclerosis. Cell Biochem Funct. 2023;41(7):779-787. PMID 37653672. Review of laboratory research on the molecular pathways through which curcumin may act in multiple sclerosis.
- Zeng L, Yang T, Yang K, et al. Curcumin and Curcuma longa Extract in the Treatment of 10 Types of Autoimmune Diseases: A Systematic Review and Meta-Analysis of 31 Randomized Controlled Trials. Front Immunol. 2022;13:896476. PMID 35979355. Meta-analysis of curcumin trials in 10 autoimmune diseases, including two in MS, calling for larger studies.
- Guan X, Wu Y, Jia Q, et al. Efficacy and safety of Chinese herbal medicine for multiple sclerosis: a systematic review and meta-analysis of randomized controlled trials. Front Pharmacol. 2025;16:1635833. PMID 41059199. 2025 meta-analysis of 28 trials (1,971 people) of Chinese herbal medicine added to MS treatment, with promising results and suboptimal trial quality.
- Hu Z, Yang X, Ho PC, et al. Herb-drug interactions: a literature review. Drugs. 2005;65(9):1239-82. PMID 15916450. Review of reported herb-drug interactions, including St John's wort lowering ciclosporin and tacrolimus levels and herbs affecting warfarin.
- Navarro VJ, Khan I, Björnsson E, et al. Liver injury from herbal and dietary supplements. Hepatology. 2017;65(1):363-373. PMID 27677775. Hepatology review of liver injury from herbal and dietary supplements, which account for about 20 percent of drug-induced liver injury in the United States.
- Saper RB, Phillips RS, Sehgal A, et al. Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA. 2008;300(8):915-23. PMID 18728265. JAMA study finding detectable lead, mercury or arsenic in about one fifth of Ayurvedic medicines purchased over the Internet.
- Smith JR, Spurrier NJ, Martin JT, et al. Prevalent use of complementary and alternative medicine by patients with inflammatory eye disease. Ocul Immunol Inflamm. 2004;12(3):203-14. PMID 15385195. Survey of 89 patients at an inflammatory eye disease clinic: 42 percent used complementary medicine, with advice that physicians ask about it.
This page is for general education and is not medical advice. Acupuncture, Ayurvedic medicine and herbal medicine are complementary therapies; they do not replace diagnosis or treatment by your physician. Do not stop or change prescribed treatment without talking to your prescriber. In an emergency call 911.


