




















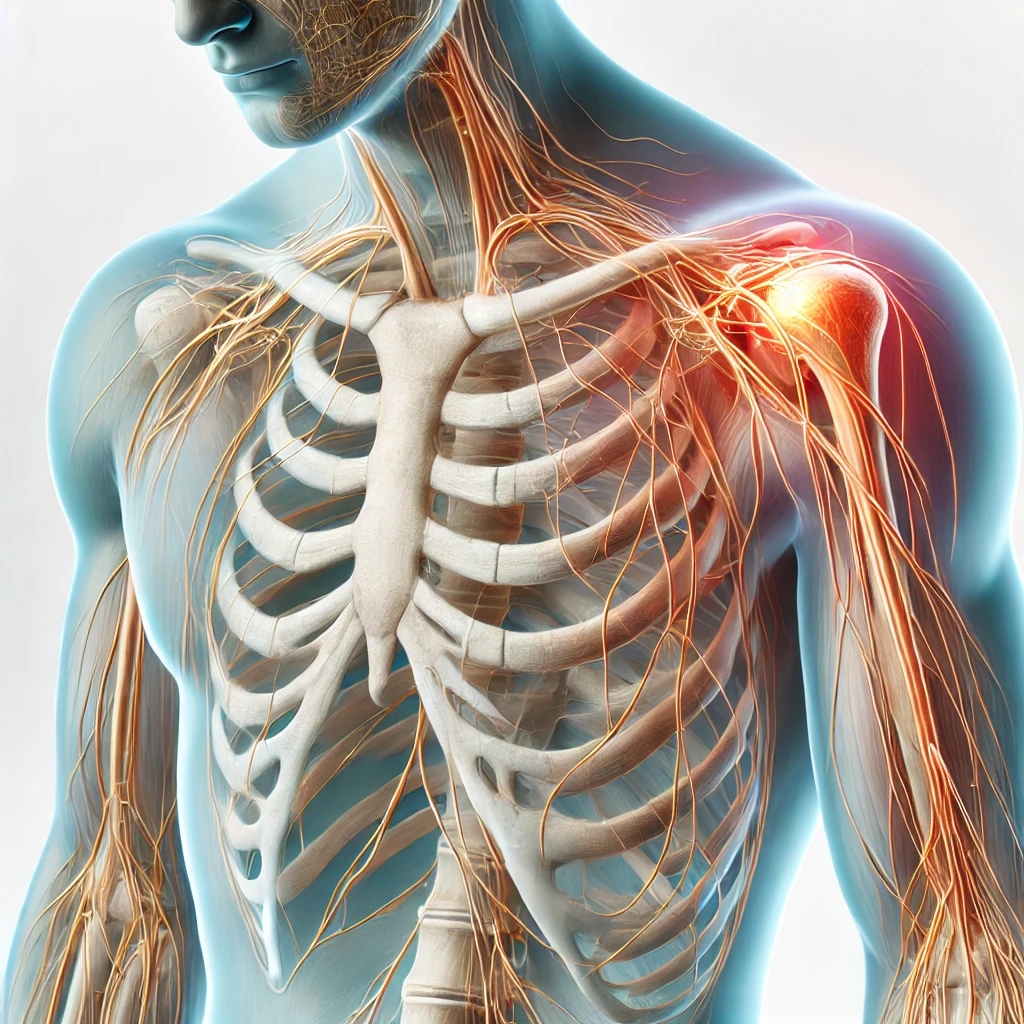
- What it is: A rare disorder of the nerves of the shoulder and arm, also called neuralgic amyotrophy or brachial neuritis, with sudden severe pain followed by weakness.
- Common symptoms: Intense shoulder or upper arm pain that can wake you from sleep, then weakness or muscle wasting, and sometimes numbness or tingling.
- Conventional care: Early corticosteroids in some cases, pain medicines, physical and occupational therapy, and surgery for selected cases with nerve constriction.
- How integrative care fits: Acupuncture and other therapies are used as supportive care for pain and stress after the condition is under medical management.
- Evidence at a glance: No controlled trials of acupuncture, Ayurveda or herbs for this condition; one acupuncture case report only. Evidence for nerve pain in general is low quality.
What is Parsonage-Turner Syndrome?
Parsonage-Turner syndrome is a condition in which the nerves of the shoulder and arm become inflamed or damaged, causing sudden severe pain followed by weakness. It is also called neuralgic amyotrophy or brachial neuritis. It is often underdiagnosed, and it has no single known cause.[1, 2]
Common symptoms
The first symptom is usually sudden, severe pain in the shoulder girdle, on one side or sometimes both. The pain often spreads to the neck, arm and forearm, and in many people it lasts from a few days to about 4 weeks.[1]
- Weakness in the shoulder or arm that appears after the pain begins[2]
- Muscle wasting in the affected area, which can develop early[3]
- Numbness or other sensory changes in some people[1]
Causes and risk factors
The cause is not fully understood. Reviews describe a combination of genetic predisposition, an immune trigger and mechanical stress on the affected nerve segments.[2] Reported triggers include infections, immunizations, injury, surgery and childbirth.[3] A rare inherited form, hereditary brachial plexus neuropathy, can look the same and tends to recur.[3]
How it is diagnosed and treated conventionally
Diagnosis is mainly clinical, supported by nerve conduction studies, needle electromyography, lab tests and imaging. Care teams need to tell it apart from similar conditions, because a wrong diagnosis can lead to unnecessary surgery.[1] MRI or high-resolution ultrasound can show hourglass-like constrictions of a nerve, which help confirm the diagnosis.[4]
Treatment depends on the phase of the illness. It often includes supportive care, physical therapy, corticosteroids and sometimes intravenous immunoglobulin.[1] Early high-dose steroids may help initial pain, but weakness and later pain respond more to time, physical therapy and non-narcotic pain medicines.[3] There are no randomized trials of treatment.[2]
Surgery may be considered when imaging shows a constricted nerve and recovery stalls.[4, 5] Many people recover well, but newer work shows that long-term pain, weakness and fatigue are common for years.[5]
Why Parsonage-Turner Syndrome calls for a whole-person approach
Parsonage-Turner syndrome is not only a problem of one nerve. The acute attack, the weeks of weakness and the long recovery all affect sleep, mood, activity and work. In one review, a quarter of untreated patients were unable to work three years later.[2]
For that reason, recovery is usually shared among several kinds of care. The factors below are the ones reviews highlight.
Nerve pain and its persistence
The severe early pain can turn into a chronic pain syndrome that needs multidimensional treatment.[2] Pain from nerve injury can also amplify through the spinal cord and brain, a process called central sensitization.[6]
Movement and fatigue
Rehabilitation aims to restore shoulder blade mechanics, conserve energy, prevent joint stiffness and manage pain.[3] Some experts advise focusing on motor coordination and pacing rather than heavy strength training, which may worsen symptoms.[5]
Immune and mechanical factors
An immune component is suggested by nerve biopsies and by triggers such as infection and immunization. Mechanical stress on the nerve also appears to matter.[2, 3]
Exercise and stress
A systematic review and expert consensus found that appropriate exercise can ease neuropathic pain in a range of conditions.[7] Parsonage-Turner syndrome was not among them, so exercise should be planned with your therapist.
Acupuncture as supportive care in Parsonage-Turner Syndrome
What the research shows
No controlled trial of acupuncture for Parsonage-Turner syndrome was found. The only report is a single case of a 26-year-old man with idiopathic brachial neuritis, diagnosed two years earlier, who improved after weekly ultrasound-guided electroacupuncture combined with daily rehabilitation. One case cannot show that acupuncture caused the improvement.[8]
For nerve pain in general, the evidence is weak. A Cochrane review of six small studies of chronic peripheral neuropathic pain found very low-quality evidence and could not support or refute acupuncture.[9] A review of non-drug treatments for painful neuropathies rated the evidence for acupuncture as weak, specifically in painful chemotherapy-induced neuropathy.[10]
Acupuncture has better support for some common chronic pain problems, including shoulder pain, in an analysis of 39 trials. These results do not tell us whether it helps nerve-related shoulder pain.[11] A review of limb musculoskeletal problems found inconsistent results for shoulder pain.[12]
How acupuncture may work
Laboratory and review work suggests acupuncture strengthens the body's descending pain-inhibiting pathways, acts through opioid and other signaling systems, and locally lowers inflammatory mediators.[6] Animal studies also point to effects on brain circuits and neuroinflammation.[13] These are proposed explanations from mostly animal research, not proof of benefit in this condition.
What treatment involves
Treatment uses fine, sterile, single-use needles, usually left in place about 20 to 40 minutes. Points are chosen for the neck, shoulder, arm and the person as a whole. We would begin only once your diagnosis is established and your physicians know about the care, then reassess after a short series of visits.
In prospective studies, about 9 in 100 patients had a minor reaction such as bleeding, soreness or redness at the needle site, and serious events occurred in about 1 in 10,000 patients.[14] Tell the practitioner first if you have a bleeding disorder, take blood thinners, are pregnant, or have a pacemaker (relevant to electroacupuncture). Needling over a weak, wasted or numb arm should be done gently and with your care team's knowledge.
Ayurvedic medicine as supportive care in Parsonage-Turner Syndrome
The Ayurvedic view
Ayurveda has no classical name for Parsonage-Turner syndrome. Practitioners usually describe sudden severe pain with later weakness and wasting as a Vata disorder, Vata being the principle said to govern movement and nerve function. Classical arm and shoulder conditions such as Vishwachi and Avabahuka are sometimes used as reference points. These are traditional categories, not biomedical diagnoses.
Therapies that may be used
Care is individualized and may include:
- Diet and daily routine intended to calm Vata, such as warm, regular meals and steady sleep hours
- Gentle warm oil massage of the neck, shoulder and arm, once acute inflammation has settled
- Herbs prescribed individually by a qualified practitioner
- Stress-reduction practices such as breathing exercises
Panchakarma is a traditional course of cleansing procedures. It is not appropriate during the acute painful phase, during pregnancy, acute illness or frailty, or when the arm is very weak. We would consider it only with your physician's agreement.
What the research shows
No clinical studies of Ayurvedic treatment for Parsonage-Turner syndrome were found. A PubMed search for Ayurveda in nerve pain and neuritis also turned up no controlled trials in this area. Ayurvedic therapies therefore have no evidence behind them for this condition, and any benefit is unknown.
Turmeric, a common Ayurvedic herb, has been reviewed in peripheral neuropathies, including laboratory and animal work, but none of that concerns Parsonage-Turner syndrome.[15] Product quality is also a concern, since about one fifth of Ayurvedic medicines bought online contained detectable lead, mercury or arsenic.[16]
Herbal medicine as supportive care in Parsonage-Turner Syndrome
Herbs and formulas that have been studied
No herb or formula has been tested in Parsonage-Turner syndrome. Studies of herbs in related nerve pain are few. A review of curcumin, from turmeric, in peripheral neuropathies describes anti-inflammatory and nerve-protective effects in laboratory and animal studies, and notes that it is poorly absorbed.[15] Nutmeg spray and St John's wort have been tested in small trials of chronic neuropathic pain.[17]
What the research shows
A Cochrane review found only two small trials of herbal products for neuropathic pain lasting three months or more. The evidence was very low quality, and the authors could not say whether nutmeg or St John's wort helps.[17] These findings concern long-standing neuropathic pain from other causes, not this condition.
Safety and herb-drug interactions
Herbs are active substances and can interact with medicines. Reviews describe interactions with warfarin, with bleeding reported for herbs including dang gui, dan shen, ginseng and ginger, and St John's wort can lower the blood levels of many drugs, including ciclosporin and tacrolimus.[18, 19] This matters if you take blood thinners, immunosuppressants or antidepressants.
About one fifth of Ayurvedic medicines bought online contained detectable lead, mercury or arsenic.[16] Herbs should come from tested sources. Tell us if you are pregnant or breastfeeding or have liver or kidney disease.
Translating traditional medicine into modern biological language
This is interpretation, not equivalence. Chinese medicine describes sudden arm pain with later weakness as obstruction of qi and blood in the channels, with weakness suggesting a deficiency. Researchers studying acupuncture for nerve pain measure things that loosely parallel this: descending pain inhibition, inflammatory mediators and central sensitization.[6]
Ayurveda's aggravated Vata describes pain, movement loss and wasting. No study has shown that a dosha corresponds to a particular biological process.
How this care fits with your medical care
This care is supportive and complementary. Keep your neurologist, physiatrist, physical or occupational therapist and primary physician, and do not stop or change prescribed medicines, including steroids, without your prescriber. For a condition like this, we ask that you are under a physician's care for it and that your treating team knows you are receiving complementary care.
Please bring your diagnosis, nerve test and imaging reports, a full list of medicines and supplements, and details of any planned surgery or immunoglobulin treatment. We do not diagnose the cause of arm pain or weakness.
When to seek urgent medical care
Sudden shoulder or arm pain with weakness needs prompt medical assessment, because other conditions can look the same.[1]
- New arm or hand weakness, or weakness that is getting worse
- Shortness of breath, especially when lying flat, which can signal involvement of the nerve to the diaphragm[3]
- Weakness or numbness in both legs, trouble walking, or new bladder or bowel changes
- Chest pain, or arm pain with sweating or breathlessness
- Fever with severe neck or arm pain
- Hoarseness or trouble swallowing that is new
If any of these occur, call 911 or go to the nearest emergency department.
Frequently asked questions
What is Parsonage-Turner Syndrome?
Parsonage-Turner syndrome, also called neuralgic amyotrophy or brachial neuritis, is a rare disorder of the nerves of the shoulder and arm. It typically starts with sudden severe pain in the shoulder or upper arm, followed by weakness and sometimes muscle wasting. The cause is not fully understood. Many people improve over months to years, though some have lasting pain or weakness.
Can acupuncture help people with Parsonage-Turner Syndrome?
We do not know. No controlled trials exist for this condition, only a single case report. Evidence for acupuncture in nerve pain in general is low quality. Some people use it as supportive care for pain and stress, always alongside medical treatment and with their physicians’ knowledge.
Does Ayurvedic or herbal medicine work for Parsonage-Turner Syndrome?
There are no studies of Ayurvedic or herbal treatment in this condition, so any benefit is unknown. Studies of herbs for other kinds of nerve pain are small and low in quality. Herbs can interact with medicines, so they should be prescribed individually and reviewed against your medicine list.
Can I stop my steroids or skip physical therapy if I have acupuncture?
No. Acupuncture, Ayurveda and herbal medicine are complementary and do not replace medical care. Do not stop or change prescribed medicines without your prescriber, and follow your care team’s advice on rehabilitation and any surgery. New or worsening weakness or breathing trouble needs prompt medical assessment.
How soon might I notice a change?
This varies and no result can be promised. Parsonage-Turner syndrome often improves slowly over months to years whatever the treatment, so it is hard to tell what causes a change. We reassess after a short series of visits to see whether supportive care is helping with pain, sleep or stress.
Does insurance cover acupuncture for Parsonage-Turner syndrome?
It may. Netra Integrative Health Clinic accepts most major insurance plans that include out-of-network acupuncture benefits, for example Aetna, Blue Cross Blue Shield, Cigna and UnitedHealthcare, and offers a free benefits check. HSA and FSA cards and CareCredit are also accepted. Call (908) 402-7301 to ask about your plan.
References
- Al Khalili Y, Jain S, Lam JC, et al. Brachial Neuritis. StatPearls [Internet]. 2024. PMID 29763017. StatPearls chapter on brachial neuritis (Parsonage-Turner syndrome) covering its unclear cause, symptoms, diagnosis and acute and chronic management.
- Holle JF, Limmroth V, Windisch W, et al. Neuralgic Amyotrophy. Dtsch Arztebl Int. 2024;121(15):483-489. PMID 38835178. Review of neuralgic amyotrophy covering its multifactorial cause, steroid treatment, absence of randomized trials, and progression to chronic pain.
- Meiling JB, Boon AJ, Niu Z, et al. Parsonage-Turner Syndrome and Hereditary Brachial Plexus Neuropathy. Mayo Clin Proc. 2024;99(1):124-140. PMID 38176820. Mayo Clinic Proceedings review of Parsonage-Turner syndrome and hereditary brachial plexus neuropathy: triggers, imaging, steroids, rehabilitation, and the phrenic nerve.
- Gstoettner C, Mayer JA, Rassam S, et al. Neuralgic amyotrophy: a paradigm shift in diagnosis and treatment. J Neurol Neurosurg Psychiatry. 2020;91(8):879-888. PMID 32487526. Review describing hourglass-like nerve constrictions seen on MRI and ultrasound, the incomplete recovery many patients have, and surgery as an option.
- Gabet JM, Anderson N, Groothuis JT, et al. Neuralgic amyotrophy: An update in evaluation, diagnosis, and treatment approaches. Muscle Nerve. 2025;71(5):846-856. PMID 39402917. 2025 review of neuralgic amyotrophy noting long-term pain, weakness and fatigue, rehabilitation emphasizing coordination and pacing, and surgical referral criteria.
- Lai HC, Lin YW, Hsieh CL. Acupuncture-Analgesia-Mediated Alleviation of Central Sensitization. Evid Based Complement Alternat Med. 2019;2019:6173412. PMID 30984277. Review of how acupuncture may relieve pain by strengthening descending inhibition, acting on opioid pathways, and lowering local inflammatory mediators.
- Zhang YH, Hu HY, Xiong YC, et al. Exercise for Neuropathic Pain: A Systematic Review and Expert Consensus. Front Med (Lausanne). 2021;8:756940. PMID 34901069. Systematic review and expert consensus finding exercise can reduce neuropathic pain across several conditions.
- Su PH, Tai CJ. A CARE-compliant article: a case report of idiopathic brachial neuritis treated with ultrasound-guided electroacupuncture. Medicine (Baltimore). 2019;98(19):e15325. PMID 31083162. Single case report of a man with idiopathic brachial neuritis who improved after ultrasound-guided electroacupuncture; cannot show cause and effect.
- Ju ZY, Wang K, Cui HS, et al. Acupuncture for neuropathic pain in adults. Cochrane Database Syst Rev. 2017;12(12):CD012057. PMID 29197180. Cochrane review of six small trials of acupuncture for chronic neuropathic pain, finding very low-quality evidence and no firm conclusion.
- Liampas A, Rekatsina M, Vadalouca A, et al. Non-Pharmacological Management of Painful Peripheral Neuropathies: A Systematic Review. Adv Ther. 2020;37(10):4096-4106. PMID 32809209. Systematic review of non-drug treatments for painful peripheral neuropathies, rating acupuncture evidence in chemotherapy-induced neuropathy as weaker than for stimulation therapies.
- Vickers AJ, Vertosick EA, Lewith G, et al. Acupuncture for Chronic Pain: Update of an Individual Patient Data Meta-Analysis. J Pain. 2018;19(5):455-474. PMID 29198932. Individual patient data meta-analysis of 39 trials finding acupuncture better than sham or no acupuncture for several chronic pain conditions including shoulder pain.
- Cox J, Varatharajan S, Côté P, et al. Effectiveness of Acupuncture Therapies to Manage Musculoskeletal Disorders of the Extremities: A Systematic Review. J Orthop Sports Phys Ther. 2016;46(6):409-29. PMID 27117725. Systematic review of acupuncture for musculoskeletal disorders of the limbs, finding inconsistent evidence overall and inconclusive results for shoulder pain.
- Su N, Cai P, Dou Z, et al. Brain nuclei and neural circuits in neuropathic pain and brain modulation mechanisms of acupuncture: a review on animal-based experimental research. Front Neurosci. 2023;17:1243231. PMID 37712096. Review of animal research on brain circuits in neuropathic pain and how acupuncture may modulate neurotransmitters and neuroinflammation.
- Bäumler P, Zhang W, Stübinger T, et al. Acupuncture-related adverse events: systematic review and meta-analyses of prospective clinical studies. BMJ Open. 2021;11(9):e045961. PMID 34489268. Systematic review of 21 prospective studies finding minor acupuncture reactions in about 9 percent of patients and serious events in about 1 per 10,000.
- Caillaud M, Aung Myo YP, McKiver BD, et al. Key Developments in the Potential of Curcumin for the Treatment of Peripheral Neuropathies. Antioxidants (Basel). 2020;9(10). PMID 33023197. Review of curcumin for peripheral neuropathies covering laboratory, animal and clinical studies, noting anti-inflammatory effects and very poor bioavailability.
- Saper RB, Phillips RS, Sehgal A, et al. Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA. 2008;300(8):915-23. PMID 18728265. JAMA study finding detectable lead, mercury or arsenic in about one fifth of Ayurvedic medicines purchased over the Internet.
- Boyd A, Bleakley C, Hurley DA, et al. Herbal medicinal products or preparations for neuropathic pain. Cochrane Database Syst Rev. 2019;4(4):CD010528. PMID 30938843. Cochrane review of herbal products for neuropathic pain finding only two small, very low-quality trials of nutmeg and St John's wort.
- Milić N, Milosević N, Golocorbin Kon S, et al. Warfarin interactions with medicinal herbs. Nat Prod Commun. 2014;9(8):1211-6. PMID 25233607. Review of reported interactions between warfarin and medicinal herbs, including bleeding events with several herbs.
- Hu Z, Yang X, Ho PC, et al. Herb-drug interactions: a literature review. Drugs. 2005;65(9):1239-82. PMID 15916450. Literature review of herb-drug interactions, including St John's wort lowering levels of ciclosporin and tacrolimus.
This page is for general education and is not medical advice. Acupuncture, Ayurvedic medicine and herbal medicine are complementary therapies; they do not replace diagnosis or treatment by your physician. Do not stop or change prescribed treatment without talking to your prescriber. In an emergency call 911.


