




















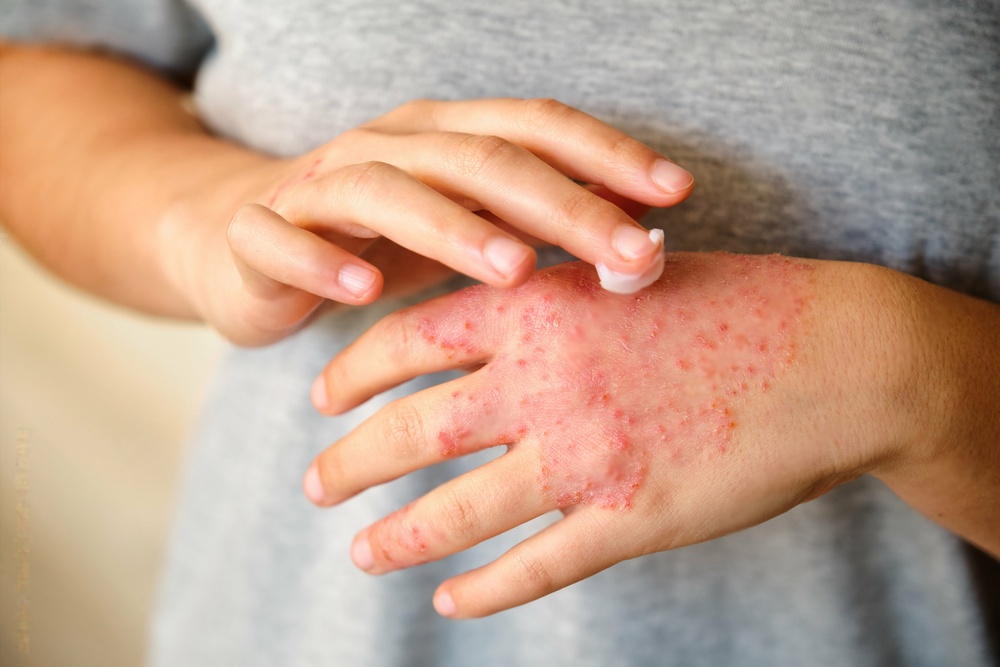
- What it is: A drug-related skin reaction of burning, itching and redness reported after stopping prolonged use of medium to high-potency topical steroids.
- Common symptoms: Redness, burning or stinging, itching, scaling, swelling and sometimes weeping skin, most often on the face and genital area.
- Conventional care: Dermatologist-guided management, gentle skin care, treating infection if it occurs, and symptom relief; the diagnosis is still debated.
- How integrative care fits: Acupuncture, Ayurvedic therapies and individually prescribed herbs may be used as supportive care for itch, sleep and stress, never for stopping or changing steroids.
- Evidence at a glance: No clinical trials for the condition itself; limited, indirect evidence for itch in eczema and for sleep problems.
What is Topical Steroid Withdrawal?
Topical steroid withdrawal (also called red skin syndrome or topical steroid addiction) is a drug-related skin reaction of burning, itching and redness that follows the sudden stopping of medium to high-potency topical steroids after prolonged use, typically at least 3 months.[1] It is a controversial diagnosis, and it is often hard to tell apart from severe eczema, so a physician needs to be involved.[2, 3]
Common symptoms
Reviews of published cases describe burning and stinging as the most frequent symptoms and redness as the most common sign.[4] Itch and scaling are also common, and swelling can occur.[4, 5]
- Intense redness and a burning or stinging feeling
- Itching, often worse at night
- Dry, flaking or peeling skin
- Swelling and, in some people, oozing or crusting
- Poor sleep, which is common in people with eczema, the condition most often behind steroid use[6]
Two patterns have been described: a papulopustular type with bumps and a redder, swollen type that causes more burning and edema.[4]
Causes and risk factors
The condition is linked to prolonged use of moderate to high-potency steroid creams, often on the face, and is reported most often in women. Many patients described using the steroids improperly, such as for cosmetic reasons.[4, 5] The face and genital area are most often affected.[1, 4]
The mechanism is not settled. One StatPearls description calls it a form of tachyphylaxis (the skin responding less to the drug) with rebound blood vessel widening and skin barrier dysfunction.[1] A 2025 pilot study of 16 patients found a distinct pattern of inflammatory and metabolic activity in the skin compared with eczema.[2]
How it is diagnosed and treated conventionally
There are no formal diagnostic criteria, and the condition overlaps with poorly controlled eczema.[7] Reviewers suggest suspecting it when long-term steroid use is followed by redness, burning or itch.[5] In 2026, a panel of 11 experienced clinicians proposed preliminary criteria that include a history of escalating steroid need, a rash that differs from the original condition, and severe burning or nerve-type pain.[3]
Treatment is guided by a dermatologist and depends on the person and the underlying skin disease. A recent review of treatments being used or studied, including natural products, lifestyle measures, acupuncture and diet changes, found that few are backed by rigorous clinical evidence.[7] Education and follow-up about proper steroid use are considered important.[5] Do not stop, taper or restart a prescribed steroid without your physician's advice.
Why Topical Steroid Withdrawal calls for a whole-person approach
Topical steroid withdrawal involves the skin barrier, blood vessels, nerves and the original skin disease, and the symptoms can affect sleep and mood. Researchers have also noted that it is difficult to separate from the eczema it often follows.
Care that eases itch, supports sleep and reduces stress may help a person cope while the dermatologist manages the skin.
The skin barrier and blood vessels
Skin barrier dysfunction and rebound widening of blood vessels are the mechanisms proposed to explain the redness, heat and burning.[1]
Nerve-type pain and burning
A consensus panel listed spontaneous nerve-type pain and severe burning of the skin among the features that help to identify the condition.[3] A 2025 pilot study described neuroinflammatory pathways in skin samples from affected patients, though it was small.[2]
Sleep
Sleep problems are very common in atopic dermatitis, the condition for which steroids are often prescribed. A meta-analysis of 32 studies found that about 43% of people with eczema had a sleep disorder.[6] Poor sleep in eczema has been linked with attention and thinking problems, and one review called for sleep management to be part of care.[8]
Stress and mood
In atopic dermatitis, a meta-analysis of eight trials found that psychological approaches such as stress management and cognitive behavioral therapy lowered eczema severity, itch and scratching, though the authors said a firm conclusion was premature.[9]
Acupuncture as supportive care in Topical Steroid Withdrawal
What the research shows
There are no clinical trials of acupuncture for topical steroid withdrawal. What exists is research on related symptoms. A 2026 review of treatments for steroid withdrawal included acupuncture among the approaches being tried and found few supported by rigorous evidence.[7]
For itch in eczema, a meta-analysis of eight trials (463 people) found lower itch and quality-of-life scores with acupuncture, with no serious adverse events, but the trials were small and limited in quality.[10] A sham-controlled trial of 36 adults with mild to moderate eczema found a larger drop in disease score with real acupuncture than with sham.[11] A larger open trial of 121 adults found no difference in overall severity at 12 weeks, though itch appeared lower with acupuncture.[12] These results come from eczema, not withdrawal.
For sleep, a review of 24 trials in insomnia found in a meta-analysis of 15 of them that acupuncture improved sleep scores compared with medicine, with benefit seen from the third week of treatment, although results varied widely between trials.[13]
How acupuncture may work
How acupuncture might help itch or sleep is not settled, and no mechanism has been shown for topical steroid withdrawal. Any effect on itch would be a general, symptom-level effect, not a change in the withdrawal process itself.
What treatment involves
Treatment uses fine, sterile, single-use needles at points on the body chosen for the individual, usually left in place for about 20 to 40 minutes. A course of several visits is usual, with reassessment. Needles are not placed through weeping, infected or broken skin, and points away from the affected areas are chosen.
Serious problems from acupuncture are rare. In prospective studies, about 9 in 100 patients had a minor reaction such as bleeding, pain or soreness at a needle site, and serious events occurred in about 1 in 10,000 patients.[14] Tell the practitioner first if you have a bleeding disorder, take blood thinners, are pregnant, or have an active skin infection.
Ayurvedic medicine as supportive care in Topical Steroid Withdrawal
The Ayurvedic view
Ayurveda has no classical name for this condition. A burning, red, inflamed and itchy skin state is traditionally understood as aggravated Pitta, sometimes with Kapha and impaired digestion. These are traditional categories used to plan care, not biomedical diagnoses.
Therapies that may be used
Care is chosen for the individual and focuses on calming the body, not on the skin alone:
- A cooling, regular diet, with less spicy, sour and fermented food
- Regular sleep hours, rest and stress-calming practices such as gentle breathing
- Bland, cooling herbal preparations applied only to intact skin, patch tested first
- Herbs such as turmeric or neem, prescribed by a qualified practitioner
Panchakarma is not appropriate here, because the skin is inflamed and fragile and the person is often exhausted, and it is also unsuitable in pregnancy, acute illness or frailty. A herbal preparation applied to the skin (transdermal medication therapy) must not be used on raw, weeping or burning skin, because many botanicals can irritate or cause allergic reactions. Herbs given by mouth can also interact with medicines, including blood thinners and antidepressants.[15]
What the research shows
There are no clinical trials of Ayurvedic treatment for topical steroid withdrawal, and none for eczema in the reviews we found. The evidence is none. Ayurvedic products also vary in quality: one study of products bought online found detectable lead, mercury or arsenic in about one fifth of them.[16]
Herbal medicine as supportive care in Topical Steroid Withdrawal
Herbs and formulas that have been studied
Chinese herbal formulas taken by mouth, bathed in or applied to the skin have been studied for atopic eczema, the condition most often behind steroid use.[17, 18] A review of traditional Chinese medicine for eczema and food allergy described a triple regimen of oral herbs, bath and cream that was reported to improve skin lesions, itch and sleep loss in people who were steroid-dependent or in topical steroid withdrawal.[19] A 2025 pilot study of 16 patients tested berberine and metformin in an open-label trial, but this was not a controlled study.[2]
What the research shows
The evidence for withdrawal itself is none from controlled trials. The report of a combined regimen came from a narrative review, not a controlled trial.[19]
For eczema, a Cochrane review of 28 trials found Chinese herbal medicine looked helpful in some comparisons, but most trials had a high risk of bias and the authors could not find conclusive evidence of benefit.[17] A meta-analysis of 10 trials of Chinese herbs applied to the skin found a higher response rate than conventional medicines but no difference in lesion scores compared with steroid creams, and again judged the trials flawed.[18]
Safety and herb-drug interactions
Herbs can interact with medicines. A literature review described serious interactions, including bleeding with blood thinners and altered levels of immune-suppressing drugs and antidepressants.[15] Inflamed skin absorbs substances differently and may react to herbal creams and washes, so new products should not be applied to raw or weeping skin. Tell us about all medicines, supplements and skin products you use, and about pregnancy, breastfeeding, and liver or kidney disease.
Herbs should come from tested sources and be prescribed individually.[16]
Translating traditional medicine into modern biological language
The links drawn here are interpretation, not equivalence. Chinese medicine often describes red, hot, itchy, burning skin as heat in the blood, sometimes with damp-heat or wind, and chronic cases as blood or yin deficiency. Ayurveda describes aggravated Pitta. Researchers studying topical steroid withdrawal measure things that loosely parallel these ideas: widened blood vessels, a disrupted skin barrier, nerve-related burning and altered inflammatory metabolism.[1, 2]
No study has shown that a TCM pattern or a dosha corresponds to a specific biological process.
How this care fits with your medical care
Our role is supportive and complementary. For a condition like this, we ask that you are under a physician's care for it and that your treating team knows you are receiving complementary care. Do not stop, taper or restart a prescribed steroid or other medicine on our advice, and we do not diagnose topical steroid withdrawal or manage the skin disease.
Please bring your diagnosis, a list of all current and past steroid creams with how long you used them, any other medicines and supplements, and recent notes from your dermatologist. Acupuncture is not done on weeping, infected or broken skin.
When to seek urgent medical care
Severe skin reactions can become serious, and some signs need prompt care.[1]
- Skin that is oozing, crusting, hot or painful, or with pus or red streaks, which may signal infection
- Fever, chills, or feeling very unwell
- Widespread, rapidly worsening redness or peeling over most of the body
- Swelling of the face, eyes or lips that interferes with vision or breathing
- Severe sleeplessness, hopelessness or thoughts of self-harm
If any of these occur, call 911 or go to the nearest emergency department. For thoughts of self-harm, call or text 988, the Suicide and Crisis Lifeline.
Frequently asked questions
What is topical steroid withdrawal?
Topical steroid withdrawal, also called red skin syndrome, is a reaction of burning, itching and redness reported after stopping prolonged use of medium to high-potency steroid creams. It most often affects the face and genital area. The diagnosis is debated and can look like severe eczema, so it should be assessed by a physician before anything else is tried.
Can acupuncture help people with topical steroid withdrawal?
There are no clinical trials of acupuncture for topical steroid withdrawal itself. Studies in eczema suggest it may lessen itch, and a review of insomnia trials suggests it may help sleep, but the research is limited and not specific to this condition. We offer it only as supportive care for itch, sleep and stress, alongside your dermatologist.
Does Ayurvedic or herbal medicine work for topical steroid withdrawal?
There are no controlled trials for this condition. Ayurveda has none for eczema in the reviews we found, and Chinese herbal medicine for eczema has weak, low-quality evidence. One review described a combined herbal regimen for steroid withdrawal, but it was not a controlled trial. Herbs can interact with medicines and irritate raw skin, so they are used with great caution.
Can I stop my steroid cream or restart it based on this care?
No. Do not stop, taper or restart any steroid or other prescribed treatment without your physician’s advice. Acupuncture, Ayurveda and herbal medicine are complementary care and do not replace your dermatologist. Signs of infection, fever, or rapidly worsening skin need prompt medical assessment.
How soon might I notice a change?
It varies from person to person and no result can be promised. Because there are no trials for this condition, there is no tested schedule. Acupuncture trials for eczema itch and insomnia used courses of several weeks. We reassess after a short course of visits to see whether treatment is helping.
Does insurance cover acupuncture for topical steroid withdrawal?
It may. Netra Integrative Health Clinic accepts most major insurance plans that include out-of-network acupuncture benefits, for example Aetna, Blue Cross Blue Shield, Cigna and UnitedHealthcare, and offers a free benefits check. HSA and FSA cards and CareCredit are also accepted. Call (908) 402-7301 to ask about your plan.
References
- Mohta A, Sathe NC. Topical Steroid Withdrawal (Red Skin Syndrome). StatPearls [Internet]. 2024. PMID 38753938. StatPearls chapter describing topical corticosteroid withdrawal as burning, itching and redness after stopping prolonged medium to high-potency steroids, with rebound vasodilation and barrier dysfunction.
- Shobnam N, Ratley G, Saksena S, et al. Topical Steroid Withdrawal Is a Targetable Excess of Mitochondrial NAD. J Invest Dermatol. 2025;145(8):1953-1968.e14. PMID 40088241. 2025 pilot study of 16 patients proposing objective criteria separating topical steroid withdrawal from eczema and a role for NAD metabolism, with an open-label berberine and metformin trial.
- Hsu C, Guo L, Adams D, et al. Topical steroid withdrawal syndrome: developing diagnostic criteria through a modified Delphi method. Br J Dermatol. 2026;194(4):768-778. PMID 41379834. 2026 Delphi consensus of 11 clinicians proposing preliminary diagnostic criteria for topical steroid withdrawal syndrome and noting difficulty distinguishing it from eczema.
- Hajar T, Leshem YA, Hanifin JM, et al. A systematic review of topical corticosteroid withdrawal ("steroid addiction") in patients with atopic dermatitis and other dermatoses. J Am Acad Dermatol. 2015;72(3):541-549.e2. PMID 25592622. 2015 systematic review of 34 studies describing steroid withdrawal mainly on the face and genitals of women, with burning and redness and two subtypes.
- Hwang J, Lio PA. Topical corticosteroid withdrawal ('steroid addiction'): an update of a systematic review. J Dermatolog Treat. 2022;33(3):1293-1298. PMID 33499686. 2022 systematic review update describing topical corticosteroid withdrawal after prolonged moderate to high-potency use, mostly on the face, with limited, biased evidence.
- Zhang N, Chi H, Jin Q, et al. Prevalence of sleep disorders in atopic dermatitis: a systematic review and meta-analysis. Arch Dermatol Res. 2025;317(1):668. PMID 40169442. Meta-analysis of 32 studies finding about 43 percent of people with atopic dermatitis have sleep disorders.
- Moon Y, Lio P. Therapeutic Update on Topical Steroid Withdrawal. Dermatitis. 2026. PMID 41612882. 2026 review of treatments used or studied for topical steroid withdrawal, including acupuncture and natural products, concluding that few have rigorous evidence.
- Khosravi A, Glińska J, Barańska-Rybak W. Sleep Efficiency and Neurocognitive Decline in Atopic Dermatitis: A Systematic Review. Acta Derm Venereol. 2024;104:adv40459. PMID 39474675. Systematic review of 13 studies linking poor sleep in atopic dermatitis with neurocognitive problems and calling for sleep management in care.
- Chida Y, Steptoe A, Hirakawa N, et al. The effects of psychological intervention on atopic dermatitis. A systematic review and meta-analysis. Int Arch Allergy Immunol. 2007;144(1):1-9. PMID 17449959. Meta-analysis of eight trials finding psychological interventions reduced eczema severity, itch and scratching, with a firm conclusion judged premature.
- Liang S, Huang KY, Zhang L, et al. Acupuncture for atopic dermatitis: a systematic review and meta-analysis. BMJ Open. 2024;14(12):e084788. PMID 39638592. 2024 meta-analysis of eight trials (463 people) of acupuncture for atopic dermatitis finding lower itch and quality-of-life scores, with limited study quality.
- Park JG, Lee H, Yeom M, et al. Effect of acupuncture treatment in patients with mild to moderate atopic dermatitis: a randomized, participant- and assessor-blind sham-controlled trial. BMC Complement Med Ther. 2021;21(1):132. PMID 33926433. Sham-controlled trial of 36 adults with mild to moderate eczema finding a larger disease-score drop with real acupuncture, without serious adverse events.
- Rotter G, Ahnert MW, Geue AV, et al. Acupuncture and osteopathic medicine for atopic dermatitis: a three-armed, randomized controlled explorative clinical trial. Clin Exp Dermatol. 2022;47(12):2166-2175. PMID 35875898. Open three-arm trial of 121 adults with atopic dermatitis finding no difference in severity at 12 weeks with acupuncture but possibly less itch.
- Kim SA, Lee SH, Kim JH, et al. Efficacy of Acupuncture for Insomnia: A Systematic Review and Meta-Analysis. Am J Chin Med. 2021;49(5):1135-1150. PMID 34049475. Meta-analysis of 24 trials of acupuncture for insomnia showing better sleep scores than medicines, with high heterogeneity.
- Bäumler P, Zhang W, Stübinger T, et al. Acupuncture-related adverse events: systematic review and meta-analyses of prospective clinical studies. BMJ Open. 2021;11(9):e045961. PMID 34489268. Systematic review of 21 prospective studies finding minor acupuncture reactions in about 9 percent of patients and serious events in about 1 per 10,000.
- Hu Z, Yang X, Ho PC, et al. Herb-drug interactions: a literature review. Drugs. 2005;65(9):1239-82. PMID 15916450. Literature review of herb-drug interactions with clinical significance, including bleeding with warfarin and altered drug levels with St. John's wort.
- Saper RB, Phillips RS, Sehgal A, et al. Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA. 2008;300(8):915-23. PMID 18728265. JAMA study finding detectable lead, mercury or arsenic in about one fifth of Ayurvedic medicines purchased over the Internet.
- Gu S, Yang AW, Xue CC, et al. Chinese herbal medicine for atopic eczema. Cochrane Database Syst Rev. 2013;2013(9):CD008642. PMID 24018636. Cochrane review of 28 trials (2,306 participants) of Chinese herbal medicine for eczema; most trials were at high risk of bias and conclusive benefit was not shown.
- Gu S, Yang AW, Li CG, et al. Topical application of Chinese herbal medicine for atopic eczema: a systematic review with a meta-analysis. Dermatology. 2014;228(4):294-302. PMID 24821063. Meta-analysis of 10 trials (1,058 participants) of topical Chinese herbal medicine for atopic eczema, with no clear advantage over steroid creams and weak methods.
- Wang Z, Wang ZZ, Geliebter J, et al. Traditional Chinese medicine for food allergy and eczema. Ann Allergy Asthma Immunol. 2021;126(6):639-654. PMID 33310179. Review of traditional Chinese medicine for food allergy and eczema, including a reported oral, bath and cream regimen used in steroid-dependent and withdrawal patients.
This page is for general education and is not medical advice. Acupuncture, Ayurvedic medicine and herbal medicine are complementary therapies; they do not replace diagnosis or treatment by your physician. Do not stop or change prescribed treatment without talking to your prescriber. In an emergency call 911.


